atomoxetine - Glenmark Pharmaceuticals Inc., USA | Glenmark Pharmaceuticals Limited

Manufacturer
Glenmark Pharmaceuticals Inc., USA | Glenmark Pharmaceuticals Limited
Effective date
2026-09-29
Label type
HUMAN PRESCRIPTION DRUG LABEL
Version
9
Source
daily-update
Hydrated at
2026-10-10 01:05:33

Label at a glance#

Productatomoxetine
Active ingredientATOMOXETINE HYDROCHLORIDE
Label structure25 sections

Boxed warning

• All atomoxetine-treated pediatric patients 6 years of age or older should be monitored and observed closely for suicidal thoughts and behavior, clinical worsening, or unusual changes in behavior, especially during the initial months of therapy or at times of dosage changes. Families and caregivers should be advised of the need for close observation and communication with the health care provider. • Consider stop...

Indications and uses

Atomoxetine capsules are indicated for the treatment of attention-deficit/hyperactivity disorder (ADHD) in adults and pediatric patients 6 years of age and older. Atomoxetine capsules is indicated as an integral part of a total treatment program for ADHD that may include other measures (psychological, educational, social) for patients with ADHD

Dosage and administration

Prior to initiating treatment with atomoxetine capsules, screen patients for a personal or family history of bipolar disorder, mania, or hypomania [see Warnings and Precautions ( 5.6 )]. Atomoxetine may be taken with or without food. Take atomoxetine capsules whole; do not open the capsules. Table 1 includes the recommended atomoxetine capsules dosage in adult patients and pediatric patients 6 years of age and old...

Label contents#

Full prescribing information#

WARNING: SUICIDAL THOUGHTS AND BEHAVIORS IN PEDIATRIC PATIENTS 6 YEARS OF AGE AND OLDER

Boxed Warning section

  • All atomoxetine-treated pediatric patients 6 years of age or older should be monitored and observed closely for suicidal thoughts and behavior, clinical worsening, or unusual changes in behavior, especially during the initial months of therapy or at times of dosage changes. Families and caregivers should be advised of the need for close observation and communication with the health care provider.
  • Consider stopping atomoxetine in patients who experience emergent suicidal thoughts and behavior [see Warnings and Precautions (5.1)].
  • Atomoxetine increased the risk of suicidal ideation in pediatric patients aged 6 years of age and older with attention-deficit/hyperactivity disorder (ADHD) in short-term studies.

1 INDICATIONS AND USAGE

INDICATIONS & USAGE SECTION

Atomoxetine capsules are indicated for the treatment of attention-deficit/hyperactivity disorder (ADHD) in adults and pediatric patients 6 years of age and older.

Atomoxetine capsules is indicated as an integral part of a total treatment program for ADHD that may include other measures (psychological, educational, social) for patients with ADHD

2 DOSAGE AND ADMINISTRATION

DOSAGE & ADMINISTRATION SECTION

2.1 Recommendations Prior to Initiating atomoxetine Treatment

SPL UNCLASSIFIED SECTION

SPL UNCLASSIFIED SECTION

Prior to initiating treatment with atomoxetine capsules, screen patients for a personal or family history of bipolar disorder, mania, or hypomania [see Warnings and Precautions (5.6)].

SPL UNCLASSIFIED SECTION

2.2 Administration Instructions

SPL UNCLASSIFIED SECTION

Atomoxetine may be taken with or without food. Take atomoxetine capsules whole; do not open the capsules.

2.6 Switching to or from a Monoamine Oxidase Inhibitor Antidepressant

SPL UNCLASSIFIED SECTION

At least 14 days must elapse between discontinuation of a monoamine oxidase inhibitor (MAOI) antidepressant and initiation of atomoxetine capsules. In addition, at least 14 days must elapse after stopping atomoxetine capsules before starting an MAOI antidepressant.

2.7 Recommendations for a Missed Dose

SPL UNCLASSIFIED SECTION

If a atomoxetine capsules dose is missed, take the dose as soon as possible, but do not take more than the prescribed total daily amount of atomoxetine capsules any 24-hour period.

2.8 Recommendations for Discontinuation

SPL UNCLASSIFIED SECTION

When discontinuing atomoxetine capsules, no taper is needed [see Drug Abuse and Dependence (9.2, 9.3)].

3 DOSAGE FORMS AND STRENGTHS

DOSAGE FORMS & STRENGTHS SECTION

Capsules

  • 10 mg of atomoxetine (Opaque White, Opaque White)
  • 18 mg of atomoxetine (Opaque Yellow, Opaque White)
  • 25 mg of atomoxetine (Opaque Blue, Opaque White)
  • 40 mg of atomoxetine (Opaque Blue, Opaque Blue)
  • 60 mg of atomoxetine (Opaque Blue, Opaque Yellow)
  • 80 mg of atomoxetine (Opaque Reddish Brown, Opaque White)
  • 100 mg of atomoxetine (Opaque Reddish Brown, Opaque Reddish Brown)

4 CONTRAINDICATIONS

CONTRAINDICATIONS SECTION

Atomoxetine capsules is contraindicated in patients:

  • With known hypersensitivity reaction to atomoxetine capsules or other constituents of atomoxetine capsules. Hypersensitivity reactions included anaphylaxis, angioneurotic edema, urticaria, and rash [see Warnings and Precautions (5.8)].
  • Taking, or within 14 days of stopping, a monoamine oxidase inhibitor (MAOI) [see Drug Interactions (7)].
  • With narrow angle glaucoma. In clinical trials, atomoxetine capsules use was associated with an increased risk of mydriasis.
  • With pheochromocytoma or a history of pheochromocytoma. Serious reactions, including elevated blood pressure and tachyarrhythmia, have been reported in patients with pheochromocytoma or a history of pheochromocytoma who received atomoxetine capsules.
  • With severe cardiac or vascular disorders whose condition would be expected to deteriorate if they had a clinically important increase in blood pressure or heart rate (e.g., 15 to 20 mm Hg in blood pressure or 20 beats per minute in heart rate) [see Warnings and Precautions (Error! Hyperlink reference not valid.)].

5 WARNINGS AND PRECAUTIONS

WARNINGS AND PRECAUTIONS SECTION

5.1 Suicidal Thoughts and Behaviors in Pediatric Patients 6 Years of Age and Older

SPL UNCLASSIFIED SECTION

  • All atomoxetine-treated pediatric patients should be monitored and observed closely for clinical worsening, suicidal thoughts and behavior, and unusual changes in behavior, especially during the initial few months of atomoxetine therapy, or at times of dosage changes, either increases or decreases.
  • Families and caregivers of atomoxetine-treated pediatric patients should be alerted about the need to monitor patients daily for the emergence of agitation, irritability, unusual changes in behavior, and mental health-related symptoms, as well as the emergence of suicidal thoughts and behavior, and to report such symptoms immediately to a health care provider.
  • Consider changing the therapeutic regimen, including stopping atomoxetine, in patients who experience emergent suicidality or symptoms that might be precursors to emerging suicidal thoughts and behavior, especially if these symptoms are severe or abrupt in onset, or were not part of the patient’s presenting symptoms.

Atomoxetine increased the risk of suicidal ideation in pediatric patients 6 years and older with ADHD in pooled placebo-controlled short-term studies (6 to 18 weeks). In 12 studies (11 studies in patients with ADHD and 1 study in another population) with over 2,200 pediatric patients, the mean incidence of suicidal ideation in atomoxetine-treated pediatric patients was 0.4% (5/1,357) (including one patient with a suicide attempt) compared to 0% (0/851) in placebo-treated pediatric patients. No suicides occurred in these studies. All the suicidal ideations occurred in pediatric patients 6 to 12 years of age, and all occurred during the first month of atomoxetine treatment. It is unknown whether the risk of suicidal ideation in pediatric patients extends to longer-term use. A similar analysis in adult patients treated with atomoxetine for ADHD did not reveal an increased risk of suicidal ideation or behavior.

The following psychiatric symptoms have been reported with atomoxetine: anxiety, agitation, panic attacks, insomnia, irritability, hostility, aggressiveness, impulsivity, akathisia (psychomotor restlessness), hypomania and mania. Although a causal link between the emergence of such symptoms and the emergence of suicidal impulses has not been established, there is a concern that such symptoms may represent precursors to emerging suicidality.

5.2 Severe Liver Injury

SPL UNCLASSIFIED SECTION

Atomoxetine should be discontinued and not restarted in patients with jaundice or laboratory evidence of liver injury, Liver enzyme and function tests should be obtained upon the first symptom or sign of liver dysfunction (e.g., pruritus, dark urine, jaundice, right upper quadrant tenderness, or unexplained “flu like” symptoms)

Postmarketing reports indicate that atomoxetine can cause severe liver injury.

Although no evidence of liver injury was detected in clinical trials of about 6,000 patients, there have been rare cases of clinically significant liver injury that were considered probably or possibly related to atomoxetine use during postmarketing use.

  • Rare cases of liver failure have been reported during postmarketing use, including a case that resulted in a liver transplant.
  • Reported cases of liver injury occurred within 120 days of initiation of atomoxetine in most cases and some patients presented with markedly elevated liver enzymes (>20 times upper limit of normal (ULN)), and jaundice with significantly elevated bilirubin levels (>2 times ULN), followed by recovery upon atomoxetine discontinuation. In one patient, liver injury, manifested by elevated hepatic enzymes up to 40 times ULN and jaundice with bilirubin up to 12 times ULN, recurred upon rechallenge, and was followed by recovery upon atomoxetine discontinuation, providing evidence that atomoxetine likely caused the liver injury. Such reactions may occur several months after atomoxetine is started, but laboratory abnormalities may continue to worsen for several weeks after atomoxetine is stopped.

5.3 Serious Cardiovascular Reactions

SPL UNCLASSIFIED SECTION

Risk Management Recommendations for Serious Cardiovascular Reactions

Prior to atomoxetine treatment, adults or pediatric patients 6 years of age or older should have a careful history (including assessment for a family history of sudden death or ventricular arrhythmia) and physical exam to assess for the presence of cardiovascular disease, and should receive further cardiac evaluation if findings suggest such disease (e.g., electrocardiogram echocardiogram).

  • Although some serious heart problems alone carry an increased risk of sudden death, atomoxetine generally should not be used in pediatric patients with known serious structural cardiac abnormalities, cardiomyopathy, serious arrhythmias, or other serious cardiac problems.
  • Consideration should be given to not treating adults with atomoxetine with clinically significant cardiac abnormalities.

Patients who develop symptoms such as exertional chest pain, unexplained syncope, or other symptoms suggestive of cardiac disease during atomoxetine treatment should stop atomoxetine and undergo a prompt cardiac evaluation.

Sudden Death and Pre-existing Structural Cardiac Abnormalities or Other Serious Heart Problems

Pediatric Patients 6 Years of Age and Older: Sudden death has been reported in association with atomoxetine treatment

at the recommended dosage in pediatric patients 6 years of age and older with structural cardiac abnormalities or other serious heart problems.

Adults: Sudden deaths, stroke, and myocardial infarction have been reported in atomoxetine-treated adults at the recommended ADHD dosage. Although the role of atomoxetine in these adult cases is also unknown, adults have a greater likelihood than pediatric patients of having serious structural cardiac abnormalities, cardiomyopathy, serious arrhythmias, coronary artery disease, or other serious cardiac problems

5.4 Increase in Blood Pressure and Heart Rate

SPL UNCLASSIFIED SECTION

atomoxetine is contraindicated in patients with severe cardiac or vascular disorders whose condition would be expected to deteriorate if they had a clinically important increase in blood pressure or heart rate Atomoxetine should be used with caution in any condition that may predispose patients to hypotension, or conditions associated with abrupt heart rate or blood pressure changes. Atomoxetine should be used with caution in patients whose underlying medical conditions could be worsened by increases in blood pressure or heart rate such as certain patients with hypertension, tachycardia, or cardiovascular or cerebrovascular disease. Heart rate and blood pressure should be measured at baseline, following atomoxetine dosage increases, and periodically while on therapy to detect possible clinically important increases in heart rate and blood pressure.

In the pediatric and adult patients in short-term, placebo-controlled clinical studies of ADHD, there were a greater proportion of atomoxetine-treated patients, compared to placebo-treated patients, who had an increase in diastolic blood pressure (DBP) ≥15 mm Hg, systolic blood pressure (SBP) ≥20 mm Hg and heart rate ≥20 bpm [see Adverse Reactions (6.1)].

Increase in Blood Pressure and Heart Rate

  • In placebo-controlled studies of pediatric patients 6 years of age and older with ADHD, tachycardia was identified as an adverse reaction in 0.3% (5/1,597) of atomoxetine-treated patients compared with 0% (0/934) of placebo-treated patients.
  • In placebo-controlled adult ADHD studies, tachycardia was identified as an adverse reaction in 1.5% (8/540) of atomoxetine-treated patients compared with 0.5% (2/402) of placebo-treated patients.
  • Orthostatic hypotension and syncope have been reported in atomoxetine-treated patients. In ADHD studies in pediatric patients 6 years of age and older, 0.2% (12/5,596) of atomoxetine-treated patients had orthostatic hypotension and 0.8% (46/5,596) had syncope. In short-term ADHD studies in pediatric patients 6 years of age and older, 1.8% (6/340) of atomoxetine-treated patients had orthostatic hypotension compared with 0.5% (1/207) of placebo-treated patients. Syncope was not reported during these studies.

Increase in Blood Pressure and Heart Rate in CYP2D6 Poor Metabolizers

  • In placebo-controlled studies of pediatric patients 6 years of age and older with ADHD, the mean heart rate increase was 9.4 beats/minute in CYP2D6 poor metabolizers and was 5 beats/minute in other CYP2D6 metabolizer types (ultrarapid, normal, and intermediate).
  • In adult clinical trials where CYP2D6 metabolizer status was available, the mean heart rate increase in CYP2D6 poor metabolizers was significantly higher than in other CYP2D6 metabolizer types (11 beats/minute versus 7.5 beats/minute, respectively).
  • In adult clinical trials where CYP2D6 metabolizer status was available, the mean change from baseline in DBP in CYP2D6 poor metabolizers was higher than in other CYP2D6 metabolizer types (4.2 versus 2.1 mm Hg) as was the mean change from baseline in SBP (CYP2D6 poor metabolizers: 2.8 versus other CYP2D6 metabolizer types: 2.4 mm Hg).

5.5 New Psychotic or Manic Symptoms and Activation of Mania

SPL UNCLASSIFIED SECTION

If psychotic or manic symptoms occur, consider discontinuing atomoxetine. Psychotic symptoms (e.g., hallucinations, delusional thinking) manic symptoms (e.g., mania) in patients without a prior history of psychotic illness or mania can be caused by atomoxetine at the recommended dosage.

5.6 Screening Patients for Bipolar Disorder

SPL UNCLASSIFIED SECTION

Before initiating treatment with atomoxetine, patients should be adequately screened for risk factors for bipolar disorder such as a personal or family history of mania and depression.

Patients with bipolar disorder or risk factors for bipolar disorder may be at increased risk of developing mania or mixed episodes during treatment with atomoxetine. It may not be possible to determine whether a manic or mixed episode that appears during treatment with atomoxetine is due to an adverse reaction to atomoxetine or a patient’s underlying bipolar disorder.

5.7 Aggressive Behavior or Hostility

SPL UNCLASSIFIED SECTION

Patients beginning treatment with atomoxetine should be monitored for the appearance or worsening of aggressive behavior or hostility.

There is evidence that atomoxetine may cause the emergence or worsening of aggressive behavior or hostility. ADHD and other mental illnesses can be associated with irritability, which can make it difficult to determine if atomoxetine or the underlying psychiatric condition is causing the emergence or worsening of aggressive behavior or hostility in specific patients. If such symptoms occur during treatment, consider a possible causal role of atomoxetine.

5.8 Hypersensitivity Reactions

SPL UNCLASSIFIED SECTION

Atomoxetine is contraindicated in patients with known hypersensitivity reaction to atomoxetine or other constituents of atomoxetine.

Although uncommon, hypersensitivity reactions, including anaphylaxis, angioneurotic edema, urticaria, and rash, have been reported in atomoxetine-treated patients.

5.9 Effects on Urine Outflow

SPL UNCLASSIFIED SECTION

A complaint of urinary retention or urinary hesitancy should be considered potentially related to atomoxetine.

In adult ADHD controlled studies, the incidence of urinary retention (1.7%, 9/540) and urinary hesitation (5.6%, 30/540) were increased among atomoxetine treated patients compared with placebo-treated patients (0%, 0/402; 0.5%, 2/402, respectively). Two atomoxetine treated adult patients and no placebo-treated patients discontinued from controlled clinical studies because of urinary retention.

5.10 Priapism

SPL UNCLASSIFIED SECTION

Prompt medical attention is required in the event of suspected priapism. in atomoxetine-treated patients.

Rare postmarketing cases of priapism, defined as painful and nonpainful penile erection lasting more than 4 hours, have been reported for pediatric and adult patients treated with atomoxetine. The erections resolved in cases in which follow-up information was available, some following discontinuation of atomoxetine.

5.11 Effect on Growth in Pediatric Patients

SPL UNCLASSIFIED SECTION

Closely monitor growth (e.g., weight, height) in pediatric patients during atomoxetine treatment.

Weight and Height in Long-Term Open-Label Studies in Pediatric Patients

Data on the long-term effects of atomoxetine on growth in pediatric patients from open-label studies in which weight and height changes were compared to normative pediatric population data. In general, the weight and height gain of atomoxetine-treated pediatric patients lagged behind that predicted by normative population data for about the first 9-12 months of treatment and subsequently (see Figure 1 below):

  • Weight gain rebounded. At about 3 years of atomoxetine treatment, patients gained a mean of 17.9 kg, which was 0.5 kg more than predicted by their baseline data.
  • Height gain stabilized. At 3 years of atomoxetine treatment, patients gained a mean of 19.4 cm, which was 0.4 cm less than predicted by their baseline data

Figure 1: Mean Weight and Height Percentiles Over Time for atomoxetine-Treated Pediatric Patients in Comparison to Normative Pediatric Population Values

figure1
figure1

After three years of atomoxetine treatment in the long-term open-label studies, patients who were:

  • Pre-pubertal at the start of treatment (girls ≤8 years old, boys ≤9 years old) gained weight and height; however, the mean weight gain was 2.1 kg less than predicted and the mean height gain was 1.2 cm less than predicted.
  • Pubertal (girls >8 to ≤13 years old, boys >9 to ≤14 years old) or late pubertal (girls >13 years old, boys >14 years old), the mean weight and height gains were close to or exceeded predicted weight and height gains.

CYP2D6 poor metabolizers and other CYP2D6 metabolizer types (ultrarapid, normal, and intermediate) treated with atomoxetine for at least two years gained weight and height. However, in:

  • CYP2D6 poor metabolizers the mean weight gain was 2.4 kg less than predicted and the mean height gain was 1.1 cm less than predicted
  • Other CYP2D6 metabolizer types the mean weight gain was 0.2 kg less than predicted and the mean height gain was 0.4 cm less than predicted.

In the long-term open-label studies, the growth pattern was generally similar regardless of pubertal status at the time of atomoxetine treatment initiation.

Weight and Height in Short-Term, Placebo-Controlled Studies in Pediatric Patients In short-term, placebo-controlled studies (up to 9 weeks), atomoxetine-treated patients lost an average of 0.4 kg in weight and gained an average of 0.9 cm in height, compared to a gain of 1.5 kg in weight and 1.1 cm in height in the placebo-treated patients.

In a fixed-dose controlled trial, 1.3%, 7.1%, 19.3%, and 29.1% of patients in the placebo, 0.5, 1.2, and 1.8 mg/kg/day atomoxetine groups, respectively, lost at least 3.5% of their body weight.

6 ADVERSE REACTIONS

ADVERSE REACTIONS SECTION

6.1 Clinical Trials Experience

SPL UNCLASSIFIED SECTION

Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice.

Atomoxetine was administered to 5,382 pediatric patients 6 years of age and older in clinical ADHD studies (Studies 1, 2, 3, 4, and 5) [see Clinical Studies (14.1)] and 1,007 adults in clinical ADHD studies (Studies 6 and 7) [see Clinical Studies(14.2)]. In the ADHD clinical trials, 2,529 pediatric patients were treated for over 6 months which included 1,625 pediatric patients who were treated for longer than 1 year.

Adverse Reactions in the Clinical Trials of Pediatric Patients 6 Years of Age and Older with ADHD

Discontinuation of Treatment Due to Adverse Reactions in the Clinical Studies of Pediatric Patients 6 Years of Age and Older:

In the acute placebo-controlled studies of pediatric patients 6 years of age and older with ADHD, 3% (48/1,613) of atomoxetine-treated pediatric patients and 1.4% (13/945) of placebo-treated pediatric patients discontinued due to an adverse reaction. Among atomoxetine-treated patients, irritability (0.3%, N=5); somnolence (0.3%, N=5); aggression (0.2%, N=4); nausea (0.2%, N=4); vomiting (0.2%, N=4); abdominal pain (0.2%, N=4); constipation (0.1%, N=2); fatigue (0.1%, N=2); feeling abnormal (0.1%, N=2); and headache (0.1%, N=2) were the reasons for discontinuation reported by more than one patient.

For all studies, (including open-label and long-term studies), 6% of atomoxetine-treated pediatric patients who were other CYP2D6 metabolizer types (ultrarapid, normal, and intermediate) and 11% of those who were CYP2D6 poor metabolizers discontinued due to an adverse reaction.

Common Adverse Reactions in the Clinical Studies of Pediatric Patients 6 Years of Age and Older: Common adverse reactions (incidence of 2% or greater in atomoxetine-treated patients and with a higher incidence in atomoxetine-treated patients compared to placebo-treated patients) in pediatric patients 6 years of age and older with ADHD are listed in Table

2. The most commonly observed adverse reactions in atomoxetine-treated patients (incidence of ≥5% and ≥ twice the incidence in placebo-treated patients), for either twice daily or once daily dosing were: nausea, vomiting, fatigue, decreased appetite, abdominal pain, and somnolence (see Tables 2 and 3).

Table 2: Common Adverse Reactionsa in Acute Studies (up to 18 weeks) in Pediatric Patients 6 Years and Older with ADHD

Adverse Reaction

Atomoxetine (N=1,597)

Placebo (N=934)

Headache

19%

15%

Abdominal painb

18%

10%

Decreased appetite

16%

4%

Somnolencec

11%

4%

Vomiting

11%

6%

Nausea

10%

5%

Fatigue

8%

3%

Irritability

6%

3%

Dizziness

5%

2%

Decreased weight

3%

0%

Anorexia

3%

1%

Rash

2%

1%

  1. a Adverse reactions reported by at least 2% of atomoxetine-treated patients and greater than placebo-treated patients. b Abdominal pain includes the terms: upper abdominal pain, and epigastric discomfort.
  2. C Somnolence includes the term sedation.

Adverse reaction in the atomoxetine-treated patients who received twice daily, and once daily dosing are shown in Table 3 (adverse reactions based on statistically significant Breslow-Day tests).

Table 3: Common Adverse Reactions in Acute Studies (up to 18 weeks) in Pediatric Patients 6 Years and Older with ADHD

Adverse Reaction

ADHD Studies with Twice Daily Dosing

ADHD Studies with Once Daily Dosing

Atomoxetine (N=715)

Placebo (N=434)

Atomoxetine (N=882)

Placebo (N=500)

Abdominal paina

17%

13%

18%

7%

Vomiting

11%

8%

11%

4%

Nausea

7%

6%

13%

4%

Fatigue

6%

4%

9%

2%

Mood swingsb

2%

0%

1%

1%

Constipationc

2%

1%

1%

0%

a Abdominal pain included the terms: upper abdominal pain, and epigastric discomfort.

  • b Mood swings didn’t meet the statistical significance on Breslow-Day test at 0.05 level, but p-value was <0.1 (trend).
  1. C Constipation didn’t meet the statistical significance on Breslow-Day test but is included in the table because of pharmacologic plausibility.

Common Adverse Reactions by CYP2D6 Metabolizer Status in the Clinical Studies of Pediatric Patients 6 Years of Age and Older: Table 4 displays adverse reactions that occurred in at least 2% of atomoxetine-treated pediatric patients who were CYP2D6 poor metabolizers and were statistically significantly more frequent in CYP2D6 poor metabolizers compared with other CYP2D6 metabolizer types (ultrarapid, normal, and intermediate).

Table 4: Common Adverse Reactionsa in atomoxetine-treated Pediatric Patients 6 Years and Older with ADHD by CYP2D6 Metabolizer Types

Adverse Reaction Atomoxetine CYP2D6 Poor Metabolizers (N=355)Atomoxetine Other CYP2D6 Metabolizer Types(N=5,019)

Insomnia

11%

6%

Decreased weight

7%

4%

Constipation

7%

4%

Depressionb

7%

4%

Tremor

5%

1%

Excoriation

4%

2%

Sedation

4%

2%

Middle insomnia

3%

1%

Conjunctivitis

3%

1%

Syncope

3%

1%

Early morning awakening

2%

1%

Mydriasis

2%

1%

  1. Adverse reactions that occurred in at least 2% of atomoxetine-treated pediatric patients who were CYP2D6 poor metabolizers and were statistically significantly more frequent in poor metabolizers compared with other CYP2D6 metabolizer types (ultrarapid, normal, and intermediate).
  2. Depression included the following terms: major depression, depressive symptoms, depressed mood, dysphoria.

Less Common Adverse Reactions in the Clinical Studies of Pediatric Patients 6 Years of Age and Older: The following reactions did not meet this criterion but were reported by more atomoxetine-treated patients than placebo-treated patients and are possibly related to atomoxetine treatment: blood pressure increased, early morning awakening (terminal insomnia), flushing, mydriasis, sinus tachycardia, asthenia, palpitations, mood swings, constipation, and dyspepsia.

The following reactions were reported by at least 2% of patients treated with atomoxetine, and equal to or less than placebo: pharyngolaryngeal pain, insomnia (insomnia includes the terms, insomnia, initial insomnia, middle insomnia). The following reaction did not meet this criterion but shows a statistically significant dose relationship: pruritus.

Seizures in the Clinical Studies of Pediatric Patients 6 Years of Age and Older: atomoxetine has not been systematically evaluated in pediatric patients with seizure disorder as these patients were excluded from atomoxetine studies. In the clinical development program, seizures were reported in 0.2% (12/5,073) of atomoxetine-treated pediatric patients whose average age was 10 years old (range 6 to 16 years of age). In these clinical trials, the seizure incidence among CYP2D6 poor metabolizers was 0.3% (1/293) compared to 0.2% (11/4,741) for other CYP2D6 metabolizer types.

Heart Rate and Blood Pressure Increases in the Clinical Studies of Pediatric Patients 6 Years of Age and Older:

Additional data from ADHD clinical trials (controlled and uncontrolled) has shown that approximately 5 to 10% of pediatric patients experienced potentially clinically important changes in heart rate (≥20 beats per minute) or blood pressure (≥15 to

20 mm Hg) [see Contraindications (4) and Warnings and Precautions (5.4)].

Adverse Reactions in the Clinical Trials of Adults with ADHD

Discontinuation of Treatment Due to Adverse Reactions in the Clinical Studies of Adults: In the acute adult placebo-controlled trials, 11.3% (61/541) atomoxetine-treated patients and 3% (12/405) placebo-treated patients discontinued for adverse reactions. Among atomoxetine-treated patients, insomnia (0.9%, N=5); nausea (0.9%, N=5); chest pain (0.6%, N=3); fatigue (0.6%, N=3); anxiety (0.4%, N=2); erectile dysfunction (0.4%, N=2); mood swings (0.4%, N=2); nervousness (0.4%, N=2); palpitations (0.4%, N=2); and urinary retention (0.4%, N=2) were the reasons for discontinuation reported by more than 1 patient.

Common Adverse Reactions in the Clinical Studies of Adults: Commonly observed adverse reactions associated with the use of atomoxetine (incidence of 2% or greater) and not observed at an equivalent incidence among placebo-treated patients (atomoxetine incidence greater than placebo) are listed in Table 5. The most commonly observed adverse reactions in patients treated with atomoxetine (incidence of 5% or greater and at least twice the incidence in placebo patients) were: constipation, dry mouth, nausea, decreased appetite, dizziness, erectile dysfunction, and urinary hesitation (see Table 5).

Table 5: Common Adverse Reactionsa Associated in Acute Studies (up to 25 weeks) of Adult Patients with ADHD

Adverse Reaction Atomoxetine (N=1,697)Placebo (N=1,560)

Nausea

26%

6%

Dry mouth

20%

5%

Decreased appetite

16%

3%

Insomniab

15%

8%

Fatigue

10%

6%

Erectile dysfunctionc

8%

1%

Constipation

8%

3%

Dizziness

8%

3%

Somnolenced

8%

5%

Abdominal paine

7%

4%

Urinary hesitationf

6%

1%

Irritability

5%

3%

Ejaculation delayedc and/or ejaculation disorderc

4%

1%

Hyperhidrosis

4%

1%

Dyspepsia

4%

2%

Vomiting

4%

2%

Abnormal dreams

4%

3%

Chills

3%

0%

Paraesthesia

3%

0%

Hot flush

3%

0%

Palpitations

3%

1%

Libido decreased

3%

1%

Sleep disorder

3%

1%

Dysmenorrheag

3%

2%

Dysuria

2%

0%

Thirst

2%

1%

Weight decreased

2%

1%

Feeling jittery

2%

1%

aReactions reported by at least 2% of patients treated with atomoxetine, and greater than placebo. The following reactions did not meet this criterion but were reported by more atomoxetine-treated patients than placebo-treated patients and are possibly related to atomoxetine treatment: peripheral coldness, tachycardia, prostatitis, testicular pain, orgasm abnormal, flatulence, asthenia, feeling cold, muscle spasm, dysgeusia, agitation, restlessness, micturition urgency, pollakiuria, pruritus, urticaria, flushing, tremor, menstruation irregular, rash, and urinary retention.

  1. b Insomnia includes the terms initial insomnia, middle insomnia, terminal insomnia and other related terms.

    c Based on total number of males (atomoxetine group, N=943; placebo group, N=869). Somnolence includes related terms.

    dAbdominal pain includes the terms: upper abdominal pain and other related terms.

    e Urinary hesitation includes the term decreased urine flow.

Common Adverse Reactions by CYP2D6 Metabolizer Status in the Clinical Studies of Adults: Table 6 displays adverse reactions that occurred in at least 2% of atomoxetine-treated adult patients who were CYP2D6 poor metabolizers and were statistically significantly more frequent compared to other CYP2D6 metabolizer types (ultrarapid, normal, and intermediate).

Table 6: Common Adverse Reactionsa in atomoxetine-treated Adult Patients with ADHD by CYP2D6 Metabolizer Types

Adverse Reaction Atomoxetine (N=1,697)Placebo (N=1,560)

Nausea

26%

6%

Dry mouth

20%

5%

Decreased appetite

16%

3%

Insomniab

15%

8%

Fatigue

10%

6%

Erectile dysfunctionc

8%

1%

Constipation

8%

3%

Dizziness

8%

3%

Somnolenced

8%

5%

Abdominal paine

7%

4%

Urinary hesitationf

6%

1%

Irritability

5%

3%

Ejaculation delayedc and/or ejaculation disorderc

4%

1%

Hyperhidrosis

4%

1%

Dyspepsia

4%

2%

Vomiting

4%

2%

Abnormal dreams

4%

3%

Chills

3%

0%

Paraesthesia

3%

0%

Hot flush

3%

0%

Palpitations

3%

1%

Libido decreased

3%

1%

Sleep disorder

3%

1%

Dysmenorrheag

3%

2%

Dysuria

2%

0%

Thirst

2%

1%

Weight decreased

2%

1%

Feeling jittery

2%

1%

  1. Adverse reactions that occurred in at least 2% of atomoxetine-treated adult patients who were CYP2D6 poor metabolizers and were statistically significantly more frequent in CYP2D6 poor metabolizers compared with other CYP2D6 metabolizer types (ultrarapid, normal, and intermediate).

Less Common Adverse Reactions in the Clinical Studies of Adults: The following reactions did not meet this criterion but were reported by more atomoxetine-treated patients than placebo-treated patients and are possibly related to atomoxetine treatment: peripheral coldness, tachycardia, prostatitis, testicular pain, orgasm abnormal, flatulence, asthenia, feeling cold, muscle spasm, dysgeusia, agitation, restlessness, micturition urgency, pollakiuria, pruritus, urticaria, flushing, tremor, menstruation irregular, rash, and urinary retention.

Seizures in the Clinical Studies of Adults: atomoxetine has not been systematically evaluated in adult patients with a seizure disorder as these patients were excluded from clinical studies during the product’s premarket testing. In the clinical development program, seizures were reported on 0.1% (1/748) of adult patients. In these clinical trials, no CYP2D6 poor metabolizers (0/43) reported seizures compared to 0.1% (1/705) for other CYP2D6 metabolizer types.

Heart Rate and Blood Pressure Increases in the Clinical Studies of Adults: Table 7 displays the proportion of atomoxetine-treated and placebo-treated patients who had an increase in diastolic blood pressure (DBP) ≥15 mm Hg, systolic blood pressure (SBP) ≥20 mm Hg, or heart rate ≥ 20 bpm in short-term, placebo-controlled clinical studies in pediatric and adult patients with ADHD [see Warnings and Precautions (5.4)].

Table 7: Proportion of ADHD Patients With an Increase of ≥ 15 mm Hg in DBP, ≥20 mm Hg in SBP, or ≥ 20 bpm in Heart Ratea

Pediatric Acute ADHD Studies

Adult Acute ADHD Studies

Maximumb

Endpoint

Maximumb

Endpoint

Atomoxetine

Placebo

Atomoxetine

Placebo

Atomoxetine

Placebo

Atomoxetine

Placebo

DBP (≥15 mm Hg)

22%

14%

9%

5%

13%

9%

5%

4%

SBP (≥20 mm Hg)

13%

9%

5%

3%

12%

8%

4%

3%

HR (≥20 bpm)

23%

12%

12%

4%

22%

8%

10%

2%

  1. Abbreviations: bpm=beats per minute; DBP=diastolic blood pressure; HR=heart rate; mm Hg=millimeters mercury; SBP=systolic blood pressure.
  2. Proportion of patients meeting threshold at any one time during the clinical studies.

Additional data from ADHD clinical trials (controlled and uncontrolled) showed that approximately 5 to 10% of adult

patients had potentially clinically important changes in heart rate (≥20 beats per minute) or blood pressure (≥15 to 20 mm

Hg) [see Contraindications (4) and Warnings and Precautions (5.4)].

Male and Female Sexual Dysfunction in the Clinical Studies of Adults: atomoxetine impaired sexual function in some patients. Estimates of the incidence of untoward sexual experience and performance in these studies are likely to underestimate their actual incidence because patients and health care providers may be reluctant to discuss them. Table 5 displays the incidence of sexual adverse reactions (reported by at least 2% of atomoxetine-treated adult patients in the placebo-controlled studies of adults with ADHD (i.e., erectile dysfunction, dysmenorrhea, and ejaculation delayed and/or ejaculation disorder).

There are no adequate and well-controlled studies examining sexual dysfunction with atomoxetine treatment. While it is difficult to know the precise risk of sexual dysfunction associated with the use of atomoxetine, health care providers should routinely inquire about sexual dysfunction.

6.2 Postmarketing Experience

SPL UNCLASSIFIED SECTION

The following adverse reactions have been identified during post approval use of atomoxetine. Unless otherwise specified, these adverse reactions have occurred in adults and pediatric patients. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure.

  • Cardiovascular system: QT prolongation, syncope.
  • Peripheral vascular effects: Raynaud's phenomenon.
  • General disorders and administration site conditions: Lethargy.
  • Musculoskeletal system: Rhabdomyolysis.
  • Nervous system disorders: Hypoaesthesia; paraesthesia in pediatric patients; sensory disturbances; tics.
  • Psychiatric disorders: Depression and depressed mood; anxiety, libido changes.
  • Seizures: Seizures have been reported and included patients with pre-existing seizure disorders, those with identified risk factors for seizures, and patients with neither a history of nor identified risk factors for seizures. The exact relationship between atomoxetine and seizures is difficult to evaluate due to uncertainty about the background risk of seizures in ADHD patients.
  • Skin and subcutaneous tissue disorders: Alopecia, hyperhidrosis.
  • Urogenital system: Male pelvic pain; urinary hesitation in pediatric patients; urinary retention in pediatric patients.

7 DRUG INTERACTIONS

DRUG INTERACTIONS SECTION

See Table 8 for clinically significant drug interactions with atomoxetine and other drugs.

Table 8: Clinically Significant Drug Interactions with atomoxetine and Other Drugs

Monoamine Oxidase Inhibitors (MAOIs)

Prevention or Management

Atomoxetine is contraindicated in patients taking MAOIs, including MAOIs such as linezolid or intravenous methylene blue, or in patients who stopped an MAOI within 14 days.

Mechanism and Clinical Effect(s)

As with other drugs affecting brain monoamine concentrations, there have been reports of serious, sometimes fatal reactions (hyperthermia, rigidity, myoclonus, autonomic instability with fluctuations of vital signs, extreme agitation progressing to delirium/coma) with concomitant use of atomoxetine and an MAOI. Some cases presented with features resembling neuroleptic malignant syndrome.

Strong CYP2D6 Inhibitors

Prevention or Management

With concomitant use of atomoxetine and a strong CYP2D6 inhibitor, increase the titration interval [see Dosage and Administration (2.5) and Clinical Pharmacology (12.3)].

Mechanism and Clinical Effect(s)

Atomoxetine is a CYP2D6 substrate. The concomitant use of atomoxetine and a strong CYP2D6 inhibitor increases atomoxetine exposure [see Clinical Pharmacology (12.3)].

Antihypertensive Drugs

Prevention or Management

Increase the frequency of monitoring blood pressure and adjust atomoxetine dosage as clinically appropriate.

Mechanism and Clinical Effect(s)

Because of increased risk of increased blood pressure, atomoxetine should be used cautiously with antihypertensive drugs, other drugs that increase blood pressure or pressor drugs (e.g., dopamine, dobutamine).

Albuterol or Other Beta2 Agonists

Prevention or Management

Increase the frequency of monitoring blood pressure and heart rate and adjust atomoxetine dosage as clinically appropriate.

Mechanism and Clinical Effect(s)

Systemically administered albuterol (e.g., oral) can be potentiated by atomoxetine, resulting in increases in heart rate and blood pressure. [see Clinical Pharmacology (12.3)].

8 USE IN SPECIFIC POPULATIONS

USE IN SPECIFIC POPULATIONS SECTION

8.1 Pregnancy

PREGNANCY SECTION

Pregnancy Exposure Registry

There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to ADHD drugs, including atomoxetine, during pregnancy. Healthcare providers are encouraged to register patients by calling the National Pregnancy Registry for ADHD Medications at 1-866-961-2388 or visiting womensmentalhealth.org/adhd-medications.

Risk Summary

Available published studies with atomoxetine use in pregnant women are insufficient to establish a drug-associated risk of major birth defects, miscarriage or adverse maternal or fetal outcomes.

Some animal reproduction studies of atomoxetine had adverse developmental outcomes. One of 3 studies in pregnant rabbits dosed during organogenesis resulted in decreased live fetuses and an increase in early resorptions, as well as slight increases in the incidences of atypical origin of carotid artery and absent subclavian artery. These effects were observed at plasma levels (AUC) 3 times and 0.4 times the human plasma levels in other CYP2D6 metabolizer types (ultrarapid, normal, and intermediate) and poor metabolizers receiving the maximum recommended human dose (MRHD), respectively. In rats dosed prior to mating and during organogenesis a decrease in fetal weight (female only) and an increase in the incidence of incomplete ossification of the vertebral arch in fetuses were observed at a dose approximately 5 times the MRHD on a mg/m2 basis. In one of 2 studies in which rats were dosed prior to mating through the periods of organogenesis and lactation, decreased pup weight and decreased pup survival were observed at doses corresponding to 5 to 6 times the MRHD on a mg/m2 basis. No adverse fetal effects were seen in pregnant rats dosed during the organogenesis period (see Data).

The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.

Data

Animal Data: Pregnant rabbits were treated with up to 100 mg/kg/day of atomoxetine by gavage throughout the period of organogenesis. At this dose, in 1 of 3 studies, a decrease in live fetuses and an increase in early resorptions was observed. Slight increases in the incidences of atypical origin of carotid artery and absent subclavian artery were observed. These findings were observed at doses that caused slight maternal toxicity. The no-effect dose for these findings was 30 mg/kg/day. The 100 mg/kg dose is approximately 23 times the MRHD on a mg/m2 basis; plasma levels (AUC) of atomoxetine at this dose in rabbits are estimated to be 3.3 times (other CYP2D6 metabolizer types) or 0.4 times (CYP2D6 poor metabolizers) those in humans receiving the MRHD.

Rats were treated with up to approximately 50 mg/kg/day of atomoxetine (approximately 6 times the MRHD on a mg/m2 basis) in the diet from 2 weeks (females) or 10 weeks (males) prior to mating through the periods of organogenesis and lactation. In 1 of 2 studies, decreases in pup weight and pup survival were observed. The decreased pup survival was also seen at 25 mg/kg (but not at 13 mg/kg). In a study in which rats were treated with atomoxetine in the diet from 2 weeks (females) or 10 weeks (males) prior to mating throughout the period of organogenesis, a decrease in fetal weight (female only) and an increase in the incidence of incomplete ossification of the vertebral arch in fetuses were observed at 40 mg/kg/day (approximately 5 times the MRHD on a mg/m2 basis) but not at 20 mg/kg/day.

No adverse fetal effects were seen when pregnant rats were treated with up to 150 mg/kg/day (approximately 17 times the MRHD on a mg/m2 basis) by gavage throughout the period of organogenesis.

8.2 Lactation

LACTATION SECTION

Risk Summary

There are no data on the presence of atomoxetine or its metabolite in human milk, the effects on the breastfed child, or the effects on milk production. Atomoxetine is present in animal milk. When a drug is present in animal milk, it is likely that the drug will be present in human milk.

The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for atomoxetine and any potential adverse effects on the breastfed child from atomoxetine or from the underlying maternal condition.

8.4 Pediatric Use

PEDIATRIC USE SECTION

The safety and effectiveness of atomoxetine for the treatment of ADHD have been established in pediatric patients 6 years of age and older. Anyone considering the use of atomoxetine in a pediatric patient should balance the potential risks with the clinical need [see Boxed Warning and Warnings and Precautions (5.1, 5.3, 5.4, 5.10)].

The atomoxetine pharmacokinetics in pediatric patients 6 years of age and older were similar to those in adults.

The safety and effectiveness of atomoxetine in pediatric patients less than 6 years of age have not been established.

Juvenile Toxicity Animal Data

A study was conducted in young rats to evaluate the effects of atomoxetine on growth and neurobehavioral and sexual development. Rats were treated with 1, 10, or 50 mg/kg/day (approximately 0.2, 2, and 8 times, respectively, the maximum human dose on a mg/m2 basis) of atomoxetine given by gavage from the early postnatal period (Day 10 of age) through adulthood. Slight delays in onset of vaginal patency (all doses) and preputial separation (10 and 50 mg/kg), slight decreases in epididymal weight and sperm number (10 and 50 mg/kg), and a slight decrease in corpora lutea (50 mg/kg) were seen, but there were no effects on fertility or reproductive performance. A slight delay in onset of incisor eruption was seen at 50 mg/kg. A slight increase in motor activity was seen on Day 15 (males at 10 and 50 mg/kg and females at 50 mg/kg) and on Day 30 (females at 50 mg/kg) but not on Day 60 of age. There were no effects on learning and memory tests. The significance of these findings to humans is unknown.

8.5 Geriatric Use

GERIATRIC USE SECTION

The safety, efficacy and pharmacokinetics of atomoxetine in geriatric patients have not been evaluated. Clinical studies of atomoxetine did not include sufficient numbers of patients 65 years of age and older to determine whether they respond differently from younger adult patients

8.6 Patients with Hepatic Impairment

SPL UNCLASSIFIED SECTION

Compared with patients with normal hepatic function atomoxetine exposure (AUC) was increased in patients with moderate (Child-Pugh Class B) (2-fold increase) and in patients with severe hepatic impairment (Child-Pugh Class C) (4fold increase). The recommended dosage in patients with moderate or severe hepatic impairment is lower than in patients with normal hepatic function [see Dosage and Administration (2.4) and Clinical Pharmacology (12.3)].

8.7 Use in Genomic Subgroups

SPL UNCLASSIFIED SECTION

The recommended titration interval (before increasing the atomoxetine dosage) is longer in CYP2D6 poor metabolizers than other CYP2D6 metabolizer types (ultrarapid, normal, and intermediate) [see Dosage and Administration (2.5)].

Atomoxetine plasma concentrations were higher in CYP2D6 poor metabolizers which may increase the risk of atomoxetine-related adverse reactions. In pediatric and adult patients, the mean heart rate was higher in CYP2D6 poor metabolizers compared to other CYP2D6 metabolizer types. In adult patients, the mean change from baseline in diastolic and systolic blood pressure was higher in CYP2D6 poor metabolizers compared to other CYP2D6 metabolizer types [see Warnings and Precautions (5.4), Clinical Pharmacology (12.3, 12.5)].

The prevalence of CYP2D6 poor metabolizers is approximately 7% in White populations, 2% in Asian populations, and 2% in Black or African American populations.

9 DRUG ABUSE AND DEPENDENCE

DRUG ABUSE AND DEPENDENCE SECTION

9.1 Controlled Substance

CONTROLLED SUBSTANCE SECTION

  • Atomoxetine is not a controlled substance.

9.2 Abuse

ABUSE SECTION

In a randomized, double-blind, placebo-controlled, abuse-potential study in adults that compared effects of atomoxetine and placebo, Atomoxetine was not associated with stimulant or euphoriant properties. Clinical study data in over 2,000 adults and pediatric patients with ADHD and over 1,200 adults with depression (atomoxetine is not indicated for the treatment of depression) showed only isolated incidents of inappropriate atomoxetine self-administration.

Drug discrimination studies in rats and monkeys showed inconsistent stimulus generalization between atomoxetine and cocaine.

9.3 Dependence

DEPENDENCE SECTION

After atomoxetine discontinuation, there was no evidence of symptom rebound or adverse reactions suggesting a atomoxetine-discontinuation or withdrawal syndrome.

10 OVERDOSAGE

OVERDOSAGE SECTION

During postmarketing use, there have been fatalities reported involving a mixed ingestion overdose of atomoxetine and at least one other drug. There have been no reports of death involving overdose of atomoxetine alone, including intentional overdoses at amounts up to 1,400 mg (14 times the maximum recommended dosage). In some cases of overdose involving atomoxetine, seizures have been reported. The most commonly reported symptoms with acute and chronic overdoses of atomoxetine were gastrointestinal symptoms, somnolence, dizziness, tremor, and abnormal behavior. Hyperactivity and agitation have also been reported. Signs and symptoms consistent with mild to moderate sympathetic nervous system activation (e.g., tachycardia, blood pressure increased, mydriasis, dry mouth) have also been observed. Most events were mild to moderate. Less commonly, there have been reports of QT prolongation and mental changes, including disorientation and hallucinations [see Clinical Pharmacology (12.2)].

If an overdose occurs, consider contacting the Poison Help line (1-800-222-1222) or a medical toxicologist for additional overdose management recommendations. Because atomoxetine is highly protein-bound, dialysis is not likely to be useful in the treatment of atomoxetine overdose.

11 DESCRIPTION

DESCRIPTION SECTION

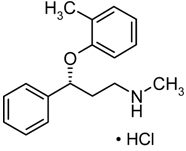
Atomoxetine is a selective norepinephrine reuptake inhibitor. Atomoxetine hydrochloride, USP is the R(-) isomer as determined by x-ray diffraction. and its chemical designation is (-)-N-Methyl-3-phenyl-3-(o-tolyloxy)-propylamine hydrochloride and its molecular formula is C17H21NO•HCl, which corresponds to a molecular weight of 291.82. The chemical structure is:

Structure
Structure

Atomoxetine hydrochloride, USP is a white to off-white crystalline powder; sparingly soluble in water.

Atomoxetine Capsules, USP are for oral administration only.

Each capsule contains atomoxetine hydrochloride USP equivalent to 10 mg, 18 mg, 25 mg, 40 mg, 60 mg, 80 mg, or 100 mg of atomoxetine. The capsules also contain pregelatinized starch.

The capsule shell for Atomoxetine Capsules, USP 10 mg contains gelatin, and titanium dioxide.

The capsule shell for Atomoxetine Capsules, USP 18 mg contains D&C Yellow No. 10, FD&C Yellow No. 6, gelatin, sodium lauryl sulfate, and titanium dioxide.

The capsule shell for Atomoxetine Capsules, USP 25 mg and 40 mg contains D&C Red No. 28, FD&C Blue No.1, gelatin, and titanium dioxide.

The capsule shell for Atomoxetine Capsules, USP 60 mg contains D&C Yellow No. 10, FD&C Blue No. 1, FD&C Red No. 3, FD&C Yellow No. 6, gelatin, sodium lauryl sulfate, and titanium dioxide.

The capsule shell for Atomoxetine Capsules, USP 80 mg and 100 mg contains D&C Red No. 28, D&C Yellow No. 10, FD&C Blue No. 1, gelatin, and titanium dioxide.

The imprinting ink for Atomoxetine Capsules, USP 10 mg, 25 mg, 40 mg, 80 mg and 100 mg has the following components: black iron oxide, D&C Yellow No. 10, FD&C Blue No. 2, FD&C Blue No. 1, FD&C Red No. 40, propylene glycol, and shellac.

The imprinting ink for Atomoxetine Capsules, USP 18 mg and 60 mg has the following components: black iron oxide, propylene glycol, potassium hydroxide, strong ammonia solution, and shellac.

12 CLINICAL PHARMACOLOGY

CLINICAL PHARMACOLOGY SECTION

12.1 Mechanism of Action

MECHANISM OF ACTION SECTION

The precise mechanism by which atomoxetine produces its therapeutic effects in ADHD is unknown, but is thought to be related to selective inhibition of the pre-synaptic norepinephrine transporter, as determined in ex vivo uptake and neurotransmitter depletion studies.

12.2 Pharmacodynamics

PHARMACODYNAMICS SECTION

An exposure-response analysis of atomoxetine (0.5, 1.2 or 1.8 mg/kg/day) or placebo demonstrated atomoxetine exposure correlates with efficacy as measured by the ADHD Rating Scale-IV-Parent Version: Investigator administered and scored. The exposure-efficacy relationship was similar to that observed between atomoxetine dosage and efficacy with median atomoxetine exposures at the two highest doses resulting in near maximal changes from baseline [see Clinical Studies (14.2)].

Cardiac Electrophysiology

The effect of atomoxetine on QTc interval prolongation was evaluated in a randomized, double-blinded, positive-(moxifloxacin 400 mg) and placebo-controlled, cross-over study in healthy male CYP2D6 poor metabolizers. A total of 120 healthy subjects were administered atomoxetine (20 mg and 60 mg) twice daily for 7 days. No large changes in QTc interval (i.e., increases >60 msec from baseline, absolute QTc >480 msec) were observed in the study. However, small changes in QTc interval cannot be excluded from this study, because the study failed to demonstrate assay sensitivity. There was a slight increase in QTc interval with increased atomoxetine concentration.

Pharmacodynamic Drug Interaction Studies

Consumption of ethanol with atomoxetine did not change the intoxicating effects of ethanol.

Concomitant use of atomoxetine with methylphenidate did not increase cardiovascular effects beyond those seen with methylphenidate alone.

  • Albuterol 600 mcg given intravenously over 2 hours (albuterol is not approved for intravenous use) induced heart rate and blood pressure increases; these effects were potentiated when co-administered with atomoxetine (60 mg twice daily for 5 days), particularly initially [see Drug Interactions (7)].

12.3 Pharmacokinetics

PHARMACOKINETICS SECTION

Pharmacokinetic parameters for atomoxetine and its metabolites in CYP2D6 poor metabolizers and other CYP2D6 metabolizer types (ultrarapid, normal, and intermediate) are presented in Table 9.

Table 9: Atomoxetine and Metabolite Pharmacokinetics in Adult CYP2D6 Poor Metabolizers and Other CYP2D6 Metabolizer Types

Parameter

Other CYP2D6 Metabolizer Typesa

CYP2D6 Poor Metabolizersb

Absorption

Dose proportionality

10-120 mg

Accumulation

1.1-fold

3.3-fold

Absolute bioavailability

63%

94%

Tmax median

1 hour

2.5 hour

Effect of Food

AUC: Unchanged; Cmax: Decreased 37%; Tmax: Delayed 3 hours

Distribution

Protein Binding

98%

Volume of distribution

0.85 L/kg

Elimination

Atomoxetine half-life

5.2 hours

21.6 hours

Atomoxetine apparent oral clearance

0.35 L/hr/kg

0.03 L/hr/kg

4-Hydroxyatomoxetine half-life

6 to 8 hours

-

N-Desmethylatomoxetine half-life

6 to 8 hours

34 to 40 hours

Metabolism

Primary metabolic pathways

CYP2D6

Other CYP enzymes

4-Hydroxyatomoxetinec concentration

1% of atomoxetine

0.1% of atomoxetined

N-Desmethylatomoxetinee concentration

5% of atomoxetine

45% of atomoxetine

Excretion

Urine

Greater than 80% of the administered dose excreted as 4-hydroxyatomoxetine-O-glucuronide; Less than 3% as unchanged drug

Feces

Less than 17% of the administered dose

Abbreviations: Cmax,ss= maximum atomoxetine plasma concentration at steady state; Tmax = time to peak concentration

  1. In this analysis, other CYP2D6 metabolizer types were defined as individuals who were not CYP2D6 poor metabolizers and included CYP2D6 ultrarapid, normal, and intermediate metabolizers.
  2. CYP2D6 poor metabolizers were defined as individuals with two nonfunctional alleles (e.g., CYP2D6*3/*4, CYP2D6*5/*5), and as a result no CYP2D6 enzyme activity.
  3. Primarily formed by CYP2D6.The major oxidative metabolite formed, regardless of CYP2D6 metabolizer type, and is further glucuronidated. 4-Hydroxyatomoxetine is equipotent to atomoxetine as an inhibitor of the norepinephrine transporter.
  4. 4-hydroxyatomoxetine is formed at a slower rate by several other cytochrome P450 enzymes.
  5. Formed by CYP2C19 and other cytochrome P450 enzymes but has substantially (20-fold) less pharmacological activity compared with atomoxetine.

Specific Populations

Hepatic Impairment: Atomoxetine exposure (AUC) was increased in subjects with moderate (Child-Pugh Class B) (2-fold increase) and severe (Child-Pugh Class C) (4-fold increase) hepatic impairment compared to subjects with normal hepatic function in other CYP2D6 metabolizer types (ultrarapid, normal, and intermediate) [see Dosage and Administration (2.4) and Use in Specific Populations (8.6)].

Renal Impairment: Patients with severe renal impairment (end stage renal disease requiring hemodialysis) had higher systemic atomoxetine exposure (about a 65% increase) than patients with normal renal function (CrCl ≥ 90 ml/minute) in other CYP2D6 metabolizer types (ultrarapid, normal, and intermediate), but there was no difference when exposure was corrected for mg/kg dose. Thus, the differences in exposure were not clinically significant.

Pediatric Patients: The pharmacokinetics of atomoxetine were evaluated in more than 400 pediatric patients in clinical studies, primarily using population pharmacokinetic modeling. Single-dose and steady-state individual pharmacokinetic data were also obtained in pediatric patients and adults. When atomoxetine doses were normalized to a mg/kg basis, similar half-life, Cmax, and AUC values were observed in pediatric patients and adults. Clearance and volume of distribution after adjustment for body weight were also similar.

Sex: Sex did not influence atomoxetine disposition.

Ethnic Origin: Ethnic origin did not influence atomoxetine disposition.

Drug Interaction Studies

Clinical Studies:

Strong CYP2D6 Inhibitors: Concomitant use of atomoxetine (20 mg BID for 5 days) with paroxetine (20 mg QD for 17 days), a known inhibitor of CYP2D6, in subjects who were not CYP2D6 poor metabolizers resulted in a 6.5-fold higher plasma exposure (AUC) to atomoxetine at steady state.

Concomitant use of atomoxetine (at sequential dosing of 10, 45, and 75 mg BID for up to 5 days of each dosage) with

fluoxetine (20 mg QD for 36 days) a known inhibitor of CYP2D6, in subjects who were not CYP2D6 poor metabolizers resulted in 6 to 8-fold increases of plasma atomoxetine exposure (AUC) at steady state compared to taking atomoxetine alone.

After concomitant use of atomoxetine with paroxetine or fluoxetine, the Css, max of atomoxetine was about 3-to 4-fold greater than the use of atomoxetine alone [see Drug Interactions (7)].

CYP3A Substrates: Concomitant use of atomoxetine (60 mg twice daily for 12 days) with midazolam (CYP3A substrate) (single dose of 5 mg), resulted in 15% increase in the midazolam AUC. This pharmacokinetic change is not clinically significant.

CYP2D6 Substrates: Concomitant use of atomoxetine (40 or 60 mg twice daily for 13 days) with desipramine, (CYP2D6 substrate) (single dose of 50 mg), did not alter the desipramine pharmacokinetics.

Drugs that Affect Gastric pH: Drugs that elevate gastric pH had no effect on atomoxetine bioavailability.

In Vitro Studies:

Drugs Highly Bound to Plasma Protein: In vitro drug-displacement studies were conducted with atomoxetine and other drugs highly bound to plasma protein at therapeutic atomoxetine concentrations. Atomoxetine did not affect the binding of warfarin, acetylsalicylic acid, phenytoin, or diazepam to human albumin. Similarly, warfarin, acetylsalicylic acid, phenytoin, or diazepam did not affect the binding of atomoxetine to human albumin.

CYP Inhibition/induction: Atomoxetine did not cause clinically important inhibition or induction of cytochrome P450 enzymes (including CYP1A2, CYP3A, CYP2D6, and CYP2C9).

12.5 Pharmacogenomics

PHARMACOGENOMICS SECTION

Atomoxetine is metabolized by CYP2D6 [see Clinical Pharmacology (12.3)]. The gene encoding CYP2D6 has variants that affect CYP2D6 metabolic function. CYP2D6 poor metabolizers are individuals with two nonfunctional alleles (e.g., CYP2D6*5/*5), and as a result have no CYP2D6 enzyme activity.

Atomoxetine AUC was approximately 10-fold higher and atomoxetine Css, max was approximately 5-fold higher in CYP2D6 poor metabolizers compared to other CYP2D6 metabolizer types [see Dosage and Administration (2.5), Warnings and Precautions (5.4), Use in Specific Populations (8.7), and Clinical Pharmacology (12.3)]. In this analysis, other CYP2D6 metabolizer types were defined as individuals who were not CYP2D6 poor metabolizers and included CYP2D6 ultrarapid, normal, and intermediate metabolizers (e.g., CYP2D6*1/*2xN, CYP2D6*1/*1, CYP2D6*1/*5, respectively).

13 NONCLINICAL TOXICOLOGY

NONCLINICAL TOXICOLOGY SECTION

13.1 Carcinogenesis, Mutagenesis, Impairment of Fertility

CARCINOGENESIS & MUTAGENESIS & IMPAIRMENT OF FERTILITY SECTION

Carcinogenesis — Atomoxetine HCl was not carcinogenic in rats and mice when given in the diet for 2 years at time-weighted average doses up to 47 and 458 mg/kg/day, respectively. The highest dose used in rats is approximately 8 and 5 times the maximum recommended human dose (MRHD) in children and adults, respectively, on a mg/m2 basis. Plasma levels (AUC) of atomoxetine at this dose in rats are estimated to be 1.8 times (other CYP2D6 metabolizer types) or 0.2 times (CYP2D6 poor metabolizers) those in humans receiving the maximum human dose. The highest dose used in mice is approximately 39 and 26 times the MRHD in children and adults, respectively, on a mg/m2 basis.

Mutagenesis — Atomoxetine HCl was negative in a battery of genotoxicity studies that included a reverse point mutation assay (Ames Test), an in vitro mouse lymphoma assay, a chromosomal aberration test in Chinese hamster ovary cells, an unscheduled DNA synthesis test in rat hepatocytes, and an in vivo micronucleus test in mice. However, there was a slight increase in the percentage of Chinese hamster ovary cells with diplochromosomes, suggesting endoreduplication (numerical aberration).

The metabolite N-desmethylatomoxetine HCl was negative in the Ames Test, mouse lymphoma assay, and unscheduled DNA synthesis test.

Impairment of Fertility — Atomoxetine HCl did not impair fertility in rats when given in the diet at doses of up to 57 mg/kg/day, which is approximately 6 times the MRHD on a mg/m2 basis.

14 CLINICAL STUDIES

CLINICAL STUDIES SECTION

14.1 ADHD Studies in Pediatric Patients 6 Years of Age and Older

SPL UNCLASSIFIED SECTION

Acute Studies in Pediatric Patients 6 Years of Age and Older with ADHD:

The effectiveness of atomoxetine in the treatment of ADHD was established in four randomized, double-blind, placebo-controlled studies of pediatric patients  6 to 18 years of age (Studies 1, 2, 3, and 4). In these studies, approximately one-third of the patients met DSM-IV criteria for inattentive subtype and two-thirds met criteria for both inattentive and hyperactive/impulsive subtypes.

In these studies, signs and symptoms of ADHD were evaluated with the investigator administered and scored ADHD Rating Scale-IV-Parent Version (ADHDRS) total score including hyperactive/impulsive and inattentive subscales by comparing the mean change from baseline to endpoint in the atomoxetine and placebo groups using an intent-to-treat (ITT) analysis (the primary endpoint). Each item on the ADHDRS maps directly to one symptom criterion for ADHD in the DSM-IV.

In Study 1, an 8-week randomized, double-blind, placebo-controlled, dose-response, acute treatment study, pediatric patients 8 to 18 years of age  (N=297), received either a fixed dosage of atomoxetine (0.25, 0.6, or 0.9 mg/kg twice daily (in the early morning and late afternoon/early evening) or placebo. Improvements in ADHD symptoms were statistically significantly superior in patients treated with either of the two higher atomoxetine dosages compared with patients treated with placebo as measured on the ADHDRS scale. The 0.9 mg/kg twice daily atomoxetine dosage did not provide any additional benefit over that observed with the 0.6 mg/kg twice daily atomoxetine dosage. The 0.25 mg/kg twice daily atomoxetine dosage group was not superior to the placebo group.

In Study 2, a 6-week randomized, double-blind, placebo-controlled, acute treatment study, pediatric patients 6 to 16 years of age  (N=171),received either atomoxetine or placebo. Atomoxetine was administered as a once daily dose in the early morning and titrated on a weight-adjusted basis according to clinical response, up to a maximum dosage of 1.5 mg/kg once daily. The mean final dosage of atomoxetine was approximately 1.3 mg/kg once daily. ADHD symptoms were statistically significantly improved in the atomoxetine group compared to the placebo group, as measured on the ADHDRS scale. Study 2 showed. that atomoxetine was effective when administered once daily in the morning.

In two identically designed, 9-week, acute, double-blind, placebo-controlled studies, pediatric patients 7 to 13 years of age (Study 3, N=147; Study 4, N=144) were randomized to receive atomoxetine, methylphenidate, or placebo. In Studies 3 and 4, atomoxetine was administered twice daily (in the early morning and late afternoon, after school) and titrated on a weight-adjusted basis according to clinical response up to the maximum recommended atomoxetine dosage of 1 mg/kg twice daily. The mean final dosage of atomoxetine in Studies 3 and 4 was approximately 0.8 mg/kg twice daily. In Studies 3 and 4, ADHD symptoms statistically significantly improved more in the atomoxetine group than the placebo group, as measured on the ADHDRS scale.

Examination of population subsets based on sex and age (<12 and 12 to 17 years of age) in these studies did not reveal any differences in response. There were not sufficient numbers of patients in racial or ethnic groups to determine if there were differences in responses in these subgroups.

Maintenance Study in Pediatric Patients 6 Years of Age and Older with ADHD

The effectiveness of atomoxetine in the maintenance treatment of ADHD in pediatric patients 6 years of age and older was established in an outpatient randomized withdrawal study of pediatric patients 6-15 years of age (Study 5). In this study, patients who met DSM-IV criteria for ADHD, and showed continuous response for about 4 weeks during an initial 10-week open-label treatment phase with atomoxetine (1.2 to 1.8 mg/kg/day) were randomized to continue of their current atomoxetine dosage (N=292) or to placebo (N=124) under double-blind treatment for observation of relapse (first double-blind phase). Response during the open-label phase was defined as CGI-ADHD-S score ≤2 and a reduction of at least 25% from baseline in ADHDRS-IV-Parent: Investigator total score.

Patients who were assigned to atomoxetine during the first double-blind phase who showed continuous response for approximately 8 months during the first double-blind treatment phase were again randomized to continue their current atomoxetine dosage (N=81) or placebo (N=82) under double-blind treatment for observation of relapse (second double-blind phase). Relapse during each of the double-blind phases was defined as CGI-ADHD-S score increases of at least 2 from the end of open-label phase and ADHDRS-IV-Parent: Investigator total score returns to ≥90% of study entry score for 2 consecutive visits.

In both double-blind phases, patients who received atomoxetine treatment experienced significantly longer times to relapse than those who received placebo.

14.2 ADHD Studies in Adults

SPL UNCLASSIFIED SECTION

The effectiveness of atomoxetine in the treatment of ADHD in adults was established in two 10-week,  randomized, double-blind, placebo-controlled clinical studies of adult patients 18 years of age and older, who met DSM-IV criteria for ADHD (Study 6, N=280; Study 7, N=256)..

In Studies 6 and 7, signs and symptoms of ADHD were evaluated using the 30-item investigator-administered Conners Adult ADHD Rating Scale Screening Version (CAARS), In these studies. the primary efficacy endpoint was the mean change from baseline to endpoint (using an ITT analysis) in the 18-item Total ADHD Symptom score (the sum of the inattentive and hyperactivity/impulsivity subscales from the CAARS .

In Studies 6 and 7, patients received either atomoxetine or placebo. Patients in the atomoxetine group received 30 mg to 60 mg twice a day (in the early morning and late afternoon/early evening) of atomoxetine which was titrated according to clinical response. The mean final atomoxetine dosage in these studies was approximately 48 mg twice daily. In both studies, ADHD symptoms were statistically significantly improved in the atomoxetine group compared to the placebo group, as measured on the ADHD Symptom score from the CAARS scale.

In Studies 6, and 7, examination of population subsets based on sex and age (<42 and ≥42 years of age) did not reveal any differences in response. There was not sufficient number of patients in racial and ethnic groups to determine if there were differences in responses among these subgroups.

14.3 Safety Studies in ADHD Patients with Tourette’s Disorder or Chronic Motor Tic Disorder OR Anxiety Disorder

SPL UNCLASSIFIED SECTION

Tics in Patients with ADHD and Tourette’s Disorder or Chronic Motor Tic Disorder

In a randomized, double-blind, placebo-controlled 18-week trial in 148 pediatric patients 7 to 17 years old with a DSM-IV diagnosis of ADHD and concurrent Tourette syndrome or chronic motor tic disorder, atomoxetine affect on tic severity was assessed. Patients in the atomoxetine group received a flexible dosage range of 0.5 to 1.5 mg/kg/day (mean dose of 1.3 mg/kg/day). In this study, 80% (n=116) of patients had Tourette’s Disorder and 20% (n=29) of patients had chronic motor tic disorder. A non-inferiority analysis revealed that atomoxetine did not worsen tics in these patients as determined by the Yale Global Tic Severity Scale Total Score (YGTSS). Out of 148 patients who entered the acute treatment phase, 103 (70%) patients discontinued the study. The primary reason for discontinuation in both the atomoxetine group (50% (38/76) and placebo group (63% (45/72) was identified lack of ADHD efficacy with most of the patients discontinuing at Week 12. There have been postmarketing reports of tics in atomoxetine-treated patients [see Adverse Reactions (6.2)].

Anxiety in Pediatric Patients with ADHD and Anxiety Disorders Two post-marketing, double-blind, placebo-controlled trials demonstrated that treating patients with ADHD and comorbid anxiety disorders with atomoxetine does not worsen their anxiety.

In a 12-week double-blind, placebo-controlled trial, 176 pediatric patients 8-17 years of age, who met DSM-IV criteria for ADHD and at least one of the anxiety disorders of separation anxiety disorder, generalized anxiety disorder or social phobia were randomized to receive atomoxetine or placebo. In the atomoxetine group, following a 2-week double-blind placebo lead-in, atomoxetine was initiated at 0.8 mg/kg/day with increase to a target dose of 1.2 mg/kg/day (median dose 1.3 mg/kg/day +/- 0.29 mg/kg/day). atomoxetine did not worsen anxiety in these patients as determined by the Pediatric Anxiety Rating Scale (PARS). Of the 158 patients who completed the double-blind placebo lead-in, 26 (16%) patients discontinued the study.

In a separate 16-week, double-blind, placebo-controlled trial, 442 patients aged 18-65, who met DSM-IV criteria for adult ADHD and social anxiety disorder (23% of whom also had Generalized Anxiety Disorder) were randomized to receive atomoxetine or placebo. In the atomoxetine group, following a 2-week double-blind placebo lead-in, atomoxetine was initiated at 40 mg/day to a maximum dosage of 100 mg/day (mean daily dose 83 mg/day +/-19.5 mg/day). atomoxetine did not worsen anxiety in these patients as determined by the Liebowitz Social Anxiety Scale (LSAS). Of the 413 patients who completed the double-blind placebo lead-in, 36% (n=149) patients discontinued the study. There have been postmarketing reports of anxiety [see Adverse Reactions (6.2)].

HOW SUPPLIED SECTION

16.1 How Supplied

Table 10 displays the available atomoxetine capsules strength

Table 10: Atomoxetine Capsules Strengths

Strength

Color

Identification

NDC

Bottles of 30 with child-resistant closure

Bottles of 1500

Bottles of 2000

10 mg

opaque white, opaque white

265/10

68462-265-30

--

68462-265-23

18 mg

opaque yellow, opaque white

266/18

68462-266-30

--

68462-266-23

25 mg

opaque blue, opaque white

267/25

68462-267-30

--

68462-267-23

40 mg

opaque blue, opaque blue

268/40

68462-268-30

--

68462-268-23

60 mg

opaque blue, opaque yellow

268/40

68462-269-30

--

68462-269-23

80 mg

opaque reddish brown, opaque white

270/80

68462-270-30

--

68462-270-23

100 mg

opaque reddish brown, opaque reddish brown

271/100

68462-271-30

68462-271-51

--

  1. a Strength is based on the base (atomoxetine).

16.2 Storage and Handling

STORAGE AND HANDLING SECTION

Store at 20°C to 25°C (68°F to 77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature].

17 PATIENT COUNSELING INFORMATION

INFORMATION FOR PATIENTS SECTION

Advise the patient to read the FDA-approved patient labeling (Medication Guide).

Suicide Risk

Patients, their families, and their caregivers should be alerted about the need to monitor patients daily for the emergence of anxiety, agitation, panic attacks, insomnia, irritability, hostility, aggressiveness, impulsivity, akathisia (psychomotor restlessness), hypomania, mania, other unusual changes in behavior, depression, and suicidal ideation, especially early during atomoxetine treatment and when the dosage is adjusted. Such symptoms should be reported to the patient's health care provider immediately [see Warnings and Precautions (5.1)].

Severe Liver Injury

Patients initiating atomoxetine capsules should be cautioned that severe liver injury may develop. Patients should be instructed to contact their healthcare provider immediately should they develop pruritus, dark urine, jaundice, right upper quadrant tenderness, or unexplained “flu-like” symptoms [see Warnings and Precautions (5.2)].

Serious Cardiovascular Reactions

Patients who develop symptoms such as exertional chest pain, unexplained syncope, or other symptoms suggestive of cardiac disease during atomoxetine treatment should stop atomoxetine and contact a health care provider [see Warnings and Precautions ( 5.3 )].

Increased Blood Pressure or Heart Rate

Atomoxetine capsules can increase blood pressure and heart rate [see Warnings and Precautions (5.4)].

Emergence of New Psychotic or Manic Symptoms and Activation of Mania

Instruct patients and their caregivers to look for signs of activation of mania/hypomania and psychosis [see Warnings and Precautions (5.5)].

Aggression or Hostility

Instruct patients and their caregivers to contact their healthcare provider as soon as possible should they notice an increase in aggression or hostility [see Warnings and Precautions (5.7)].

Priapism

The parents or guardians of pediatric patients taking atomoxetine capsules and adult patients taking atomoxetine capsules should be instructed that priapism requires prompt medical attention [see Warnings and Precautions (5.10)].

Ocular Irritant

Atomoxetine is an ocular irritant. Atomoxetine capsules are not intended to be opened. In the event of capsule content coming in contact with the eye, the affected eye should be flushed immediately with water, and medical advice obtained. Hands and any potentially contaminated surfaces should be washed as soon as possible.

Drug-Drug Interactions

Patients should be instructed to consult a healthcare provider if they are taking or plan to take any prescription or over-the-counter drugs, dietary supplements, or herbal remedies [see Drug Interactions (7)].

Sexual Dysfunction

Advise patients that atomoxetine capsules may impair sexual function. Advise patients if they experience sexual dysfunction, they should contact their health care provider [see Adverse Reactions (6.1)].

Pregnancy Registry

Advise patients that there is a pregnancy registry that monitors pregnancy outcomes in women exposed to atomoxetine capsules during pregnancy [see Use in Specific Populations (8.1)].

Food

Patients may take atomoxetine capsules with or without food.

Missed Dose

If patients miss a dose, they should be instructed to take it as soon as possible, but should not take more than the prescribed total daily amount of atomoxetine capsules in any 24-hour period.

Somnolence

The incidence of somnolence was higher in atomoxetine-treated patients than placebo-treated patients [see Adverse Reactions (6.1)]. Patients should be instructed to use caution when driving a car or operating hazardous machinery until they are reasonably certain that their performance is not affected by atomoxetine capsules.

Distributed by:

logo1
logo1

Glenmark Pharmaceuticals Inc., USA

Elmwood Park, NJ 07407

Questions? 1 (888) 721-7115

www.glenmarkpharma-us.com

July 2026

MEDICATION GUIDE Atomoxetine (A-toe-MOX-e-teen) Capsules, USP

SPL MEDGUIDE SECTION

What is the most important information I should know about atomoxetine capsules? Atomoxetine capsules can cause serious side effects, including:

  • Suicidal thoughts and actions in children 6 years of age and older. atomoxetine capsules can increase the risk of suicidal thoughts and actions in children ages 6 and older with attention deficit hyperactivity disorder (ADHD), especially within the first few months of treatment or when the dose is changed.
  • How can I watch for and try to prevent suicidal thoughts and actions?
    1. Pay close attention to, and tell your healthcare provider right away about, any changes, especially sudden changes, in mood, behavior, actions, thoughts, or feelings, or suicidal thoughts or actions. This is very important when atomoxetine capsules is started or when the dose is changed.
    2. Keep all follow-up visits with the healthcare provider as scheduled. Tell your healthcare provider about symptoms between visits as needed, especially if you have concerns.
  • Tell your healthcare provider right away if any of the following symptoms develop during treatment, especially if they are new, worse, or worry you:
  • anxiety
  • feeling agitated or restless
  • panic attacks
  • trouble sleeping
  • irritability
  • hostility or being angry or violent
  • acting aggressive
  • impulsivity
  • suicide attempts
  • extreme increase in activity or talking (mania)
  • depression
  • thoughts about suicide or dying
  • panic attacks
  • other unusual changes in mood or behavior
  • unusual decrease in activity (hypomania)


  • restlessness or feeling like you have to move

See “What are the possible side effects of atomoxetine capsules?” for more information about side effects.

What is atomoxetine capsules?

Atomoxetine capsules is a prescription medicine used to treat ADHD in adults and children 6 years of age and older. atomoxetine capsules may help increase attention and decrease impulsiveness and hyperactivity in people with ADHD.

Atomoxetine capsules should be used as a part of a total treatment program for ADHD that may include counseling or other therapies.

It is not known if atomoxetine capsules is safe and effective in children less than 6 years old.

Who should not take atomoxetine capsules?

Do not take atomoxetine capsules if you or your child:

  • are allergic to atomoxetine or any of the ingredients in atomoxetine capsules. See the end of this Medication Guide for a complete list of ingredients in atomoxetine capsules.
  • are taking or have stopped taking within the past 14 days a medicine called a monoamine oxidase inhibitor (MAOI).
  • have an eye problem called narrow angle glaucoma.
  • have or had a rare tumor called pheochromocytoma.
  • have severe heart or blood vessel problems that could get worse if your blood pressure or heart rate increases.

Before taking atomoxetine capsules, tell your healthcare provider about all medical conditions, including if you or your child:

  • have, or have a family history of, suicide thoughts or attempts, bipolar disorder, depression, mania, or hypomania.
  • have liver problems.
  • have, or have a family history of, heart problems, heart defects, irregular heartbeat, or sudden death.
  • have high blood pressure or low blood pressure.
  • have problems urinating such as trouble starting urination, weak stream, or not fully emptying the bladder.
  • have glaucoma.
  • are pregnant or plan to become pregnant. It is not known if atomoxetine capsules will harm the unborn baby.
    • Tell your healthcare provider right away if you or your child become pregnant or plan to become pregnant during treatment with atomoxetine capsules.
    • There is a pregnancy exposure registry for women who are exposed to ADHD medicines, including atomoxetine capsules, during pregnancy. The purpose of the registry is to collect information about the health of women exposed to atomoxetine capsules and their baby. If you or your child become pregnant during treatment with atomoxetine capsules, talk to your healthcare provider about registering with the National Pregnancy Registry of ADHD Medications at 1-866-961-2388 or visit online at womensmentalhealth.org/adhdmedications
  • are breastfeeding or plan to breastfeed. It is not known if atomoxetine capsules passes into the breast milk. Talk to your healthcare provider about the best way to feed the baby during treatment with atomoxetine capsules.

Tell your healthcare provider about all the medicines that you or your child take, including prescription and over-the-counter medicines, vitamins, and herbal supplements. atomoxetine capsules and some medicines may interact with each other and cause serious side effects. Your healthcare provider will decide whether atomoxetine capsules can be taken with other medicines.

Especially tell your healthcare provider if you or your child take:

  • a MAOI, including linezolid and intravenous methylene blue
  • medicines that increase or decrease blood pressure
  • asthma medicines

Know the medicines you or your child take. Keep a list of your medicines to show your healthcare provider and pharmacist. Do not start any new medicines during treatment with atomoxetine capsules without talking to your healthcare provider first.

How should I take atomoxetine capsules?

  • Take atomoxetine capsules exactly as your healthcare provider tells you. Your healthcare provider may adjust the dose until it is right for you or your child.
  • Take atomoxetine capsules with or without food.
  • Swallow atomoxetine capsules whole. Do not open the capsules.
  • atomoxetine capsules is usually taken 1 time a day in the morning, or 2 times a day, in the morning and in the late afternoon or early evening.
  • If you miss a dose of atomoxetine capsules, take the dose as soon as possible. Do not take more atomoxetine capsules than your healthcare provider prescribes in a 24-hour period.
  • If you take too much atomoxetine capsules, call your healthcare provider or Poison Help line at 1-800-222-1222 or go to the nearest emergency room right away.

What should I avoid while taking atomoxetine capsules?

  • Do not drive or operate heavy machinery until you know how atomoxetine capsules affects you. atomoxetine capsules can cause sleepiness.
  • Do not get atomoxetine capsules in or near the eyes. atomoxetine capsules can irritate the eyes. If atomoxetine capsules gets into the eyes, rinse them with water right away and tell your healthcare provider. If a capsule breaks, avoid touching the contents

and wash your hands and any surfaces that they come in contact with as soon as possible.

What are possible side effects of atomoxetine capsules?

Atomoxetine capsules can cause serious side effects, including:

  • See “What is the most important information I should know about atomoxetine capsules?”
  • Severe liver damage. Your healthcare provider will check the blood levels of liver enzymes if symptoms of liver damage develop. Tell your healthcare provider right away if any of the following symptoms develop at any time during treatment:
  • itching
  • right upper stomach pain
  • dark urine
  • the skin or the white part of the eyes turns yellow
  • unexplained flu-like symptoms
  • Serious heart-related side effects. atomoxetine capsules may increase the risk of serious heart problems including sudden death, heart attack, and stroke in adults and children who have serious heart problems or heart defects. Your healthcare provider should check for heart problems before starting treatment with atomoxetine capsules. Stop taking atomoxetine capsules and tell your healthcare provider or get medical help right away if any of the following symptoms develop during treatment:
  • chest pain
  • numbness of weakness, especially on one side of the body
  • loss of consciousness (fainting)
  • slurred speech
  • shortness of breath
  • vision changes
  • heart palpitations or fast heart rate
  • severe headache
  • Increases in blood pressure and heart rate. Your healthcare provider should check blood pressure and heart rate before starting treatment, if the dose is increased, and as needed during treatment.
  • New psychotic problems, manic symptoms, or mania episodes. People with bipolar disorder, or who have a higher risk of developing bipolar disorder, have an increased risk of developing mania. Tell your healthcare provider if any of the following symptoms develop during treatment:
  • greatly increased energy
  • severe trouble sleeping
  • racing thoughts
  • reckless behavior
  • unusually grand ideas
  • excessive happiness or irritability
  • talking more or faster than usual
  • seeing or hearing things that are not real (hallucinations)
  • unusual decrease in activity
  • depression
  • Aggressive behavior or hostility. New or worsening aggressive behavior or hostility can happen during treatment.
  • Allergic reactions. Tell your healthcare provider right away if trouble breathing, hives, rash, or swelling of the face, eyes, lips, or throat develop during treatment.
  • Problems with urination. atomoxetine capsules may cause problems with urination including decreased urine flow or trouble starting urination (urinary hesitation) or being unable to pass any urine (urinary retention). Tell your healthcare provider if any problems with urination develop during treatment.
  • Painful and prolonged erections (priapism). Priapism has happened in male children and adults who take atomoxetine capsules. Priapism is a serious problem that can cause lasting damage to the penis and may require surgery. Tell your healthcare provider and get medical help right away if you or your child develop priapism during treatment.
  • Effect on growth (height and weight) in children. Children should have their height and weight checked often during treatment.

The most common side effects of atomoxetine capsules in children include:

  • nausea
  • decreased appetite
  • vomiting
  • stomach (abdominal) pain
  • tiredness
  • sleepiness

The most common side effects of atomoxetine capsules in adults include:

  • constipation
  • dizziness
  • dry mouth
  • erectile dysfunction
  • nausea
  • urinary hesitation
  • decreased appetite

Atomoxetine capsules may cause sexual problems (dysfunction). Talk to your healthcare provider if any of the following symptoms develop:

Symptoms in males may include:

  • Symptoms in females may include:
  • delayed ejaculation or inability to have an ejaculation
  • decreased sex drive
  • decreased sex drive
  • delayed orgasm or inability to have an orgasm
  • problems getting or keeping an erection

Your healthcare provider may stop atomoxetine capsules treatment if serious side effects develop during treatment.

These are not all of the possible side effects atomoxetine capsules. Call your doctor for medical advice about side effects. You may report side effects to FDA at 1-800-FDA-1088.

How should I store atomoxetine capsules?

  • Store atomoxetine capsules at room temperature between 59 to 86°F (15 to 30°C).
  • Keep atomoxetine capsules and all medicines out of the reach of children

General information about safe and effective use of atomoxetine capsules.

Medicines are sometimes prescribed for purposes other than those listed in a Medication Guide. Do not use atomoxetine capsules for a condition for which it was not prescribed. Do not give atomoxetine capsules to other people, even if they have the same condition. It may harm them. You can ask your pharmacist or healthcare provider for information about atomoxetine capsules that is written for health professionals

What are the ingredients in atomoxetine capsules?

Active ingredient: atomoxetine hydrochloride, USP.

Inactive ingredients: pregelatinized starch, gelatin, and titanium dioxide. The capsule shell for atomoxetine capsules USP, 18 mg contains D&C Yellow No. 10, FD&C Yellow No. 6, gelatin, sodium lauryl sulfate, and titanium dioxide.

The capsule shell for atomoxetine capsules, USP 25 mg and 40 mg contains D&C Red No. 28, FD&C Blue No.1, gelatin, and titanium dioxide.

The capsule shell for atomoxetine capsules, USP 60 mg contains D&C Yellow No. 10, FD&C Blue No. 1, FD&C Red No. 3, FD&C Yellow No. 6, gelatin, sodium lauryl sulfate, and titanium dioxide.

The capsule shell for atomoxetine capsules, USP 80 mg and 100 mg contains D&C Red No. 28, D&C Yellow No. 10, FD&C Blue No. 1, gelatin, and titanium dioxide.

The imprinting ink for atomoxetine capsules, USP 10 mg, 25 mg, 40 mg, 80 mg, and 100 mg has the following components: black iron oxide, D&C Yellow No. 10, FD&C Blue No. 2, FD&C Blue No. 1, FD&C Red No. 40, methanol, propylene glycol, and shellac.

The imprinting ink for atomoxetine capsules, USP 18 mg and 60 mg has the following components: black iron oxide, propylene glycol, potassium hydroxide, strong ammonia solution, and shellac.

All trademarks are the property of their respective owners.

Distributed by:

logo2
logo2

Glenmark Pharmaceuticals Inc., USA

Elmwood Park, NJ 07407

Questions? 1 (888) 721-7115

www.glenmarkpharma-us.com

This Medication Guide has been approved by the U.S. Food and Drug Administration. Revised: 07/2026

Principle Panel Display

PACKAGE LABEL.PRINCIPAL DISPLAY PANEL

10mg-label
10mg-label

Principle Panel Display

PACKAGE LABEL.PRINCIPAL DISPLAY PANEL

18mg-label
18mg-label

Principle Panel Display

PACKAGE LABEL.PRINCIPAL DISPLAY PANEL

25mg-label
25mg-label

Principle Panel Display

PACKAGE LABEL.PRINCIPAL DISPLAY PANEL

40mg-label
40mg-label

Principle Panel Display

PACKAGE LABEL.PRINCIPAL DISPLAY PANEL

60mg-label
60mg-label

Principle Panel Display

PACKAGE LABEL.PRINCIPAL DISPLAY PANEL

80mg-label
80mg-label

Principle Panel Display

PACKAGE LABEL.PRINCIPAL DISPLAY PANEL

100mg-label
100mg-label

Product Linked Resources#

Resource, Code type, Value table
ResourceCode typeValueEquivalent identifiersSource image
BarcodeEAN-130368462265307GTIN-13: 0368462265307
EAN-13: 0368462265307
GTIN-12: 368462265307
UPC-A: 368462265307
GTIN storage (14 digits): 00368462265307
10mg-label.jpg
BarcodeEAN-130368462266304GTIN-13: 0368462266304
EAN-13: 0368462266304
GTIN-12: 368462266304
UPC-A: 368462266304
GTIN storage (14 digits): 00368462266304
18mg-label.jpg
BarcodeEAN-130368462267301GTIN-13: 0368462267301
EAN-13: 0368462267301
GTIN-12: 368462267301
UPC-A: 368462267301
GTIN storage (14 digits): 00368462267301
25mg-label.jpg
BarcodeEAN-130368462268308GTIN-13: 0368462268308
EAN-13: 0368462268308
GTIN-12: 368462268308
UPC-A: 368462268308
GTIN storage (14 digits): 00368462268308
40mg-label.jpg
BarcodeEAN-130368462269305GTIN-13: 0368462269305
EAN-13: 0368462269305
GTIN-12: 368462269305
UPC-A: 368462269305
GTIN storage (14 digits): 00368462269305
60mg-label.jpg
BarcodeEAN-130368462270301GTIN-13: 0368462270301
EAN-13: 0368462270301
GTIN-12: 368462270301
UPC-A: 368462270301
GTIN storage (14 digits): 00368462270301
80mg-label.jpg
BarcodeEAN-130368462271308GTIN-13: 0368462271308
EAN-13: 0368462271308
GTIN-12: 368462271308
UPC-A: 368462271308
GTIN storage (14 digits): 00368462271308
100mg-label.jpg

DailyMed Product Concepts#

Product concept, Relation, Version table
Product conceptRelationVersionEffective
6c13b22c-b3ba-4127-b768-0132dd5ab0d1Product name120230829
0d16f546-db6a-1939-50fc-d06382424c97Product name420210903
7792dadb-52b6-46b6-8fdf-80b1171065b5Product name120180810

DailyMed Billing Units#

Package NDC, Billing unit, Product NDC table
Package NDCBilling unitProduct NDCDailyMed indexing SPLSPL versionEffective
68462-265-30EA - Each68462-2658ec4fe7f-6559-423e-8897-ff5e86e9a8b912017-06-15
68462-266-30EA - Each68462-26688325624-e1a6-4071-821c-fbffd6de182912017-06-15
68462-267-30EA - Each68462-267bb6fd6e0-bdf4-4e72-9e23-dfbbdb6a22f712017-06-15
68462-268-30EA - Each68462-26817d177a5-ebad-497a-801a-55ecb3c50fff12017-06-15
68462-269-30EA - Each68462-2695295935f-ec36-424a-ba5e-01b7385ffe5c12017-06-15
68462-270-30EA - Each68462-270b8b528ea-989f-42eb-9ae7-36fb24fc27e312017-06-15
68462-271-30EA - Each68462-2717259d0c7-9e5e-45a2-a0f6-9db65cfcffa512017-06-15

Products#

Every source-derived product name is available through these pages.

DailyMed product names page 1 of 1 · 22 matching rows.

NDC Codes#

Ingredients#

Every source-derived ingredient row is available through these pages.

DailyMed ingredient rows page 1 of 3 · 106 matching rows.

Source Document#

Source XML

Older Hydrated Versions#

Version, Effective date, Source table
VersionEffective dateSourceHydrated
82026-08-18daily-update2026-09-05 01:02:38
72026-01-07full-release2026-05-31 21:54:20

Orange Book application contexts#

All distinct exact application/product contexts derived from this label’s complete NDC list are paginated below.

Orange Book application contexts page 1 of 1 · 1 matching rows.

Source provenance: Browse the complete Orange Book source catalog · source snapshot 43.

Orange Book products#

Current product rows page 1 of 1 · 7 matching rows.

Application-product, Trade name, Ingredient table
Application-productTrade nameIngredientStrengthDosage form / routeTE codesRLD / RSApproval date
A079019-001ATOMOXETINE HYDROCHLORIDEATOMOXETINE HYDROCHLORIDEEQ 10MG BASECAPSULE / ORALAB2017-05-30
A079019-002ATOMOXETINE HYDROCHLORIDEATOMOXETINE HYDROCHLORIDEEQ 18MG BASECAPSULE / ORALAB2017-05-30
A079019-003ATOMOXETINE HYDROCHLORIDEATOMOXETINE HYDROCHLORIDEEQ 25MG BASECAPSULE / ORALAB2017-05-30
A079019-004ATOMOXETINE HYDROCHLORIDEATOMOXETINE HYDROCHLORIDEEQ 40MG BASECAPSULE / ORALAB2017-05-30
A079019-005ATOMOXETINE HYDROCHLORIDEATOMOXETINE HYDROCHLORIDEEQ 60MG BASECAPSULE / ORALAB2017-05-30
A079019-006ATOMOXETINE HYDROCHLORIDEATOMOXETINE HYDROCHLORIDEEQ 80MG BASECAPSULE / ORALAB2017-05-30
A079019-007ATOMOXETINE HYDROCHLORIDEATOMOXETINE HYDROCHLORIDEEQ 100MG BASECAPSULE / ORALAB2017-05-30

Therapeutic equivalence codes#

Current TE-code rows page 1 of 1 · 7 matching rows.

Application-product, TE code table
Application-productTE code
A079019-001AB
A079019-002AB
A079019-003AB
A079019-004AB
A079019-005AB
A079019-006AB
A079019-007AB

Observed Orange Book product history#

Observed FDA ZIP history: Each table is queried independently by exact application/product key from successfully parsed Orange Book snapshots. Capture times identify archived source observations; absence or a change between snapshots is not inferred. FDA publication files that were not recoverable as structured ZIP data are not represented as states.

Product history page 1 of 8 · 301 observed states.

Captured, Edition, Application-product table
CapturedEditionApplication-productTrade nameStrengthDosage form / routeProduct TE source textRLD / RSApproval dateSource SHA-256
2026-09-14 22:38:342026-08A079019-001ATOMOXETINE HYDROCHLORIDEEQ 10MG BASECAPSULE / ORALAB2017-05-3084e616aacf4f…
2026-09-14 22:38:342026-08A079019-002ATOMOXETINE HYDROCHLORIDEEQ 18MG BASECAPSULE / ORALAB2017-05-3084e616aacf4f…
2026-09-14 22:38:342026-08A079019-003ATOMOXETINE HYDROCHLORIDEEQ 25MG BASECAPSULE / ORALAB2017-05-3084e616aacf4f…
2026-09-14 22:38:342026-08A079019-004ATOMOXETINE HYDROCHLORIDEEQ 40MG BASECAPSULE / ORALAB2017-05-3084e616aacf4f…
2026-09-14 22:38:342026-08A079019-005ATOMOXETINE HYDROCHLORIDEEQ 60MG BASECAPSULE / ORALAB2017-05-3084e616aacf4f…
2026-09-14 22:38:342026-08A079019-006ATOMOXETINE HYDROCHLORIDEEQ 80MG BASECAPSULE / ORALAB2017-05-3084e616aacf4f…
2026-09-14 22:38:342026-08A079019-007ATOMOXETINE HYDROCHLORIDEEQ 100MG BASECAPSULE / ORALAB2017-05-3084e616aacf4f…
2026-08-18 06:07:402026-07A079019-001ATOMOXETINE HYDROCHLORIDEEQ 10MG BASECAPSULE / ORALAB2017-05-30caaa826d4ba7…
2026-08-18 06:07:402026-07A079019-002ATOMOXETINE HYDROCHLORIDEEQ 18MG BASECAPSULE / ORALAB2017-05-30caaa826d4ba7…
2026-08-18 06:07:402026-07A079019-003ATOMOXETINE HYDROCHLORIDEEQ 25MG BASECAPSULE / ORALAB2017-05-30caaa826d4ba7…
2026-08-18 06:07:402026-07A079019-004ATOMOXETINE HYDROCHLORIDEEQ 40MG BASECAPSULE / ORALAB2017-05-30caaa826d4ba7…
2026-08-18 06:07:402026-07A079019-005ATOMOXETINE HYDROCHLORIDEEQ 60MG BASECAPSULE / ORALAB2017-05-30caaa826d4ba7…
2026-08-18 06:07:402026-07A079019-006ATOMOXETINE HYDROCHLORIDEEQ 80MG BASECAPSULE / ORALAB2017-05-30caaa826d4ba7…
2026-08-18 06:07:402026-07A079019-007ATOMOXETINE HYDROCHLORIDEEQ 100MG BASECAPSULE / ORALAB2017-05-30caaa826d4ba7…
2026-02-19 14:30 UTC2026-02A079019-001ATOMOXETINE HYDROCHLORIDEEQ 10MG BASECAPSULE / ORALAB2017-05-30011fe1cb6892…
2026-02-19 14:30 UTC2026-02A079019-002ATOMOXETINE HYDROCHLORIDEEQ 18MG BASECAPSULE / ORALAB2017-05-30011fe1cb6892…
2026-02-19 14:30 UTC2026-02A079019-003ATOMOXETINE HYDROCHLORIDEEQ 25MG BASECAPSULE / ORALAB2017-05-30011fe1cb6892…
2026-02-19 14:30 UTC2026-02A079019-004ATOMOXETINE HYDROCHLORIDEEQ 40MG BASECAPSULE / ORALAB2017-05-30011fe1cb6892…
2026-02-19 14:30 UTC2026-02A079019-005ATOMOXETINE HYDROCHLORIDEEQ 60MG BASECAPSULE / ORALAB2017-05-30011fe1cb6892…
2026-02-19 14:30 UTC2026-02A079019-006ATOMOXETINE HYDROCHLORIDEEQ 80MG BASECAPSULE / ORALAB2017-05-30011fe1cb6892…
2026-02-19 14:30 UTC2026-02A079019-007ATOMOXETINE HYDROCHLORIDEEQ 100MG BASECAPSULE / ORALAB2017-05-30011fe1cb6892…
2025-12-14 10:44 UTC · 2 captures of this ZIP2025-12A079019-001ATOMOXETINE HYDROCHLORIDEEQ 10MG BASECAPSULE / ORALAB2017-05-3031067a03dcf5…
2025-12-14 10:44 UTC · 2 captures of this ZIP2025-12A079019-002ATOMOXETINE HYDROCHLORIDEEQ 18MG BASECAPSULE / ORALAB2017-05-3031067a03dcf5…
2025-12-14 10:44 UTC · 2 captures of this ZIP2025-12A079019-003ATOMOXETINE HYDROCHLORIDEEQ 25MG BASECAPSULE / ORALAB2017-05-3031067a03dcf5…
2025-12-14 10:44 UTC · 2 captures of this ZIP2025-12A079019-004ATOMOXETINE HYDROCHLORIDEEQ 40MG BASECAPSULE / ORALAB2017-05-3031067a03dcf5…
2025-12-14 10:44 UTC · 2 captures of this ZIP2025-12A079019-005ATOMOXETINE HYDROCHLORIDEEQ 60MG BASECAPSULE / ORALAB2017-05-3031067a03dcf5…
2025-12-14 10:44 UTC · 2 captures of this ZIP2025-12A079019-006ATOMOXETINE HYDROCHLORIDEEQ 80MG BASECAPSULE / ORALAB2017-05-3031067a03dcf5…
2025-12-14 10:44 UTC · 2 captures of this ZIP2025-12A079019-007ATOMOXETINE HYDROCHLORIDEEQ 100MG BASECAPSULE / ORALAB2017-05-3031067a03dcf5…
2025-08-23 18:47 UTC2025-08A079019-001ATOMOXETINE HYDROCHLORIDEEQ 10MG BASECAPSULE / ORALAB2017-05-306a471c1ec25d…
2025-08-23 18:47 UTC2025-08A079019-002ATOMOXETINE HYDROCHLORIDEEQ 18MG BASECAPSULE / ORALAB2017-05-306a471c1ec25d…
2025-08-23 18:47 UTC2025-08A079019-003ATOMOXETINE HYDROCHLORIDEEQ 25MG BASECAPSULE / ORALAB2017-05-306a471c1ec25d…
2025-08-23 18:47 UTC2025-08A079019-004ATOMOXETINE HYDROCHLORIDEEQ 40MG BASECAPSULE / ORALAB2017-05-306a471c1ec25d…
2025-08-23 18:47 UTC2025-08A079019-005ATOMOXETINE HYDROCHLORIDEEQ 60MG BASECAPSULE / ORALAB2017-05-306a471c1ec25d…
2025-08-23 18:47 UTC2025-08A079019-006ATOMOXETINE HYDROCHLORIDEEQ 80MG BASECAPSULE / ORALAB2017-05-306a471c1ec25d…
2025-08-23 18:47 UTC2025-08A079019-007ATOMOXETINE HYDROCHLORIDEEQ 100MG BASECAPSULE / ORALAB2017-05-306a471c1ec25d…
2025-03-22 03:13 UTC · 3 captures of this ZIP2025-03A079019-001ATOMOXETINE HYDROCHLORIDEEQ 10MG BASECAPSULE / ORALAB2017-05-30fd3edfee7708…
2025-03-22 03:13 UTC · 3 captures of this ZIP2025-03A079019-002ATOMOXETINE HYDROCHLORIDEEQ 18MG BASECAPSULE / ORALAB2017-05-30fd3edfee7708…
2025-03-22 03:13 UTC · 3 captures of this ZIP2025-03A079019-003ATOMOXETINE HYDROCHLORIDEEQ 25MG BASECAPSULE / ORALAB2017-05-30fd3edfee7708…
2025-03-22 03:13 UTC · 3 captures of this ZIP2025-03A079019-004ATOMOXETINE HYDROCHLORIDEEQ 40MG BASECAPSULE / ORALAB2017-05-30fd3edfee7708…
2025-03-22 03:13 UTC · 3 captures of this ZIP2025-03A079019-005ATOMOXETINE HYDROCHLORIDEEQ 60MG BASECAPSULE / ORALAB2017-05-30fd3edfee7708…

Observed Orange Book normalized TE history#

Normalized TE history page 1 of 8 · 301 observed states.

Captured, Edition, Application-product table
CapturedEditionApplication-productTE codeOrderSource SHA-256
2026-09-14 22:38:342026-08A079019-001AB184e616aacf4f…
2026-09-14 22:38:342026-08A079019-002AB184e616aacf4f…
2026-09-14 22:38:342026-08A079019-003AB184e616aacf4f…
2026-09-14 22:38:342026-08A079019-004AB184e616aacf4f…
2026-09-14 22:38:342026-08A079019-005AB184e616aacf4f…
2026-09-14 22:38:342026-08A079019-006AB184e616aacf4f…
2026-09-14 22:38:342026-08A079019-007AB184e616aacf4f…
2026-08-18 06:07:402026-07A079019-001AB1caaa826d4ba7…
2026-08-18 06:07:402026-07A079019-002AB1caaa826d4ba7…
2026-08-18 06:07:402026-07A079019-003AB1caaa826d4ba7…
2026-08-18 06:07:402026-07A079019-004AB1caaa826d4ba7…
2026-08-18 06:07:402026-07A079019-005AB1caaa826d4ba7…
2026-08-18 06:07:402026-07A079019-006AB1caaa826d4ba7…
2026-08-18 06:07:402026-07A079019-007AB1caaa826d4ba7…
2026-02-19 14:30 UTC2026-02A079019-001AB1011fe1cb6892…
2026-02-19 14:30 UTC2026-02A079019-002AB1011fe1cb6892…
2026-02-19 14:30 UTC2026-02A079019-003AB1011fe1cb6892…
2026-02-19 14:30 UTC2026-02A079019-004AB1011fe1cb6892…
2026-02-19 14:30 UTC2026-02A079019-005AB1011fe1cb6892…
2026-02-19 14:30 UTC2026-02A079019-006AB1011fe1cb6892…
2026-02-19 14:30 UTC2026-02A079019-007AB1011fe1cb6892…
2025-12-14 10:44 UTC · 2 captures of this ZIP2025-12A079019-001AB131067a03dcf5…
2025-12-14 10:44 UTC · 2 captures of this ZIP2025-12A079019-002AB131067a03dcf5…
2025-12-14 10:44 UTC · 2 captures of this ZIP2025-12A079019-003AB131067a03dcf5…
2025-12-14 10:44 UTC · 2 captures of this ZIP2025-12A079019-004AB131067a03dcf5…
2025-12-14 10:44 UTC · 2 captures of this ZIP2025-12A079019-005AB131067a03dcf5…
2025-12-14 10:44 UTC · 2 captures of this ZIP2025-12A079019-006AB131067a03dcf5…
2025-12-14 10:44 UTC · 2 captures of this ZIP2025-12A079019-007AB131067a03dcf5…
2025-08-23 18:47 UTC2025-08A079019-001AB16a471c1ec25d…
2025-08-23 18:47 UTC2025-08A079019-002AB16a471c1ec25d…
2025-08-23 18:47 UTC2025-08A079019-003AB16a471c1ec25d…
2025-08-23 18:47 UTC2025-08A079019-004AB16a471c1ec25d…
2025-08-23 18:47 UTC2025-08A079019-005AB16a471c1ec25d…
2025-08-23 18:47 UTC2025-08A079019-006AB16a471c1ec25d…
2025-08-23 18:47 UTC2025-08A079019-007AB16a471c1ec25d…
2025-03-22 03:13 UTC · 3 captures of this ZIP2025-03A079019-001AB1fd3edfee7708…
2025-03-22 03:13 UTC · 3 captures of this ZIP2025-03A079019-002AB1fd3edfee7708…
2025-03-22 03:13 UTC · 3 captures of this ZIP2025-03A079019-003AB1fd3edfee7708…
2025-03-22 03:13 UTC · 3 captures of this ZIP2025-03A079019-004AB1fd3edfee7708…
2025-03-22 03:13 UTC · 3 captures of this ZIP2025-03A079019-005AB1fd3edfee7708…

openFDA label cross-check#

OpenFDA label data provides additional search and identifier links. DailyMed’s Structured Product Label is the canonical label on FDA.report. Matching records are deduplicated before they are shown below.

Matched openFDA labels page 1 of 1 · 1 matching rows.

Brand, Generic, Manufacturer table
BrandGenericManufacturerSPL set IDEffective dateAvailable safety fieldsJoin
atomoxetineATOMOXETINEGlenmark Pharmaceuticals Inc., USA0ab8d905-e890-4e91-a730-3e5d12f5c23f2026-08-18Boxed warning, Warnings, Adverse reactionsExact identifier
ndc (package): 68462-266-23
ndc (package): 68462-266-30
ndc (package): 68462-265-30
ndc (package): 68462-271-51
ndc (package): 68462-269-30
ndc (package): 68462-269-23
ndc (package): 68462-267-30
ndc (package): 68462-265-23
ndc (package): 68462-267-23
ndc (package): 68462-270-30
ndc (package): 68462-270-23
ndc (package): 68462-268-23
ndc (package): 68462-271-30
ndc (package): 68462-268-30
ndc (product): 68462-270
ndc (product): 68462-269
ndc (product): 68462-268
ndc (product): 68462-266
ndc (product): 68462-271
ndc (product): 68462-267
ndc (product): 68462-265
ndc11 (package): 68462027130
ndc11 (package): 68462026923
ndc11 (package): 68462026530
ndc11 (package): 68462026730
ndc11 (package): 68462026823
ndc11 (package): 68462027030
ndc11 (package): 68462026723
ndc11 (package): 68462026830
ndc11 (package): 68462026630
ndc11 (package): 68462026623
ndc11 (package): 68462026523
ndc11 (package): 68462027023
ndc11 (package): 68462026930
ndc11 (package): 68462027151
spl set id: 0ab8d905-e890-4e91-a730-3e5d12f5c23f

Reported adverse events (FAERS/openFDA)#

Adverse event summaries are temporarily unavailable. Other product information remains available.