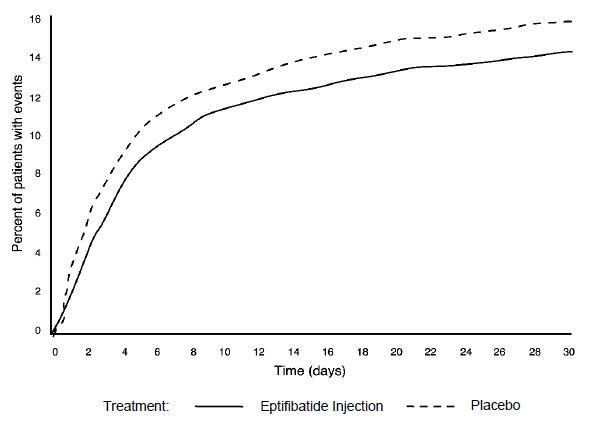
IMPACT II (Eptifibatide Injection to MinimizePlatelet Aggregation and Prevent Coronary Thrombosis II)
IMPACT II was a multicenter, double-blind,randomized, placebo-controlled study conducted in the United States in 4,010patients undergoing PCI. Major exclusion criteria included a history ofbleeding diathesis, major surgery within 6 weeks of treatment, gastrointestinalbleeding within 30 days, any stroke or structural CNS abnormality, uncontrolledhypertension, PT >1.2 times control, hematocrit <30%, platelet count<100,000/mm3, and pregnancy. Patient age ranged from 24 to 89 (mean 60)years, and 75% were male.
The patients were 92% Caucasian, 5% Black, and 3%Hispanic. Forty-one percent of the patients underwent PCI for ongoing ACS.Patients were randomly assigned to 1 of 3 treatment regimens, eachincorporating a bolus dose initiated immediately prior to PCI followed by acontinuous infusion lasting 20 to 24 hours:
- 135 mcg/kg bolus followed by a continuous infusion of 0.5 mcg/kg/min of eptifibatide injection (135/0.5);
- 135 mcg/kg bolus followed by a continuous infusion of 0.75 mcg/kg/min of eptifibatide injection (135/0.75); or
- a matching placebo bolus followed by a matching placebo continuous infusion.
Each patient received aspirin and an intravenous heparin bolus of100 units/kg, with additional bolus infusions of up to 2,000 additional unitsof heparin every 15 minutes to maintain an ACT of 300 to 350 seconds.
The primary endpoint was the composite of death, MI, or urgentrevascularization, analyzed at 30 days after randomization in all patients whoreceived at least 1 dose of study drug.
As shown in Table 7, each eptifibatide injection regimen reduced the rate ofdeath, MI, or urgent intervention, although at 30 days, this finding wasstatistically significant only in the lower-dose eptifibatide injection group.As in the PURSUIT study, the effects of eptifibatide injection were seen earlyand persisted throughout the 30-day period.
Table 7: ClinicalEvents in the IMPACT II Study
|
Placebo
n(%) |
Eptifibatide injection
(135 mcg/kg bolus then
0.5 mcg/kg/min infusion)
n (%) |
Eptifibatide injection
(135 mcg/kg bolus then
0.75 mcg/kg/min infusion)
n (%) |
| Patients |
1,285 |
1,300 |
1,286 |
| Abrupt Closure |
65 (5.1%) |
36 (2.8%) |
43 (3.3%) |
p-value versus placebo | |
0.003 |
0.003 |
| Death, MI, or Urgent Intervention | |
|
|
24 hours |
123 (9.6%) |
86 (6.6%) |
89 (6.9%) |
p-value versus placebo | |
0.006 |
0.014 |
48 hours |
131 (10.2%) |
99 (7.6%) |
102 (7.9%) |
p-value versus placebo | |
0.021 |
0.045 |
30 days (primary endpoint) |
149 (11.6%) |
118 (9.1%) |
128 (10%) |
p-value versus placebo | |
0.035 |
0.179 |
| Death or MI |
|
|
|
30 days |
110 (8.6%) |
89 (6.8%) |
95 (7.4%) |
p-value versus placebo | |
0.102 |
0.272 |
6 months |
151 (11.9%)* |
136 (10.6%)* |
130 (10.3%)* |
p-value versus placebo | |
0.297 |
0.182 |
| * Kaplan-Meier estimate of event rate. |
ESPRIT (Enhanced Suppression of the Platelet IIb/IIIa Receptor with Eptifibatide Injection Therapy)
The ESPRIT study was a multicenter, double-blind, randomized, placebo-controlled study conducted in the United States and Canada that enrolled 2,064 patients undergoing elective or urgent PCI with intended intracoronary stent placement. Exclusion criteria included MI within the previous 24 hours, ongoing chest pain, administration of any oral antiplatelet or oral anticoagulant other than aspirin within 30 days of PCI (although loading doses of thienopyridine on the day of PCI were encouraged), planned PCI of a saphenous vein graft or subsequent “staged” PCI, prior stent placement in the target lesion, PCI within the previous 90 days, a history of bleeding diathesis, major surgery within 6 weeks of treatment, gastrointestinal bleeding within 30 days, any stroke or structural CNS abnormality, uncontrolled hypertension, PT >1.2 times control, hematocrit <30%, platelet count <100,000/mm3, and pregnancy.
Patient age ranged from 24 to 93 (mean 62) years, and 73% of patients were male. The study enrolled 90% Caucasian, 5% African American, 2% Hispanic, and 1% Asian patients. Patients received a wide variety of stents. Patients were randomized either to placebo or eptifibatide injection administered as an intravenous bolus of 180 mcg/kg followed immediately by a continuous infusion of 2 mcg/kg/min, and a second bolus of 180 mcg/kg administered 10 minutes later (180/2/180). Eptifibatide infusion was continued for 18 to 24 hours after PCI or until hospital discharge, whichever came first. Each patient received at least 1 dose of aspirin (162 to 325 mg) and 60 units/kg of heparin as a bolus (not to exceed 6,000 units) if not already receiving a heparin infusion. Additional boluses of heparin (10 to 40 units/kg) could be administered in order to reach a target ACT between 200 and 300 seconds.
The primary endpoint of the ESPRIT study was the composite of death, MI, urgent target vessel revascularization (UTVR), and “bailout” to open-label eptifibatide injection due to a thrombotic complication of PCI (TBO) (e.g., visible thrombus, “no reflow,” or abrupt closure) at 48 hours. MI, UTVR, and TBO were evaluated by a blinded Clinical Events Committee.
As shown in Table 8, the incidence of the primary endpoint and selected secondary endpoints was significantly reduced in patients who received eptifibatide injection. A treatment benefit in patients who received eptifibatide injection was seen by 48 hours and at the end of the 30-day observation period.
Table 8: Clinical Events in the ESPRIT Study
| |
Placebo
(n=1,024) |
Eptifibatide injection*
(n=1,040) |
Relative Risk
(95% CI) | p-value
|
| Death, MI, UTVR, or Thrombotic “Bailout” | | | | |
| 48 hours (primary endpoint) |
108 (10.5%) |
69 (6.6%) |
0.629 (0.471, 0.84) |
0.0015 |
| 30 days |
120 (11.7%) |
78 (7.5%) |
0.64 (0.488, 0.84) | 0.0011 |
| Death, MI, or UTVR | | | | |
| 48 hours |
95 (9.3%) |
62 (6%) | 0.643 (0.472, 0.875) |
0.0045 |
| 30 days (key secondary endpoint) |
107 (10.4%) |
71 (6.8%) |
0.653 (0.49, 0.871) |
0.0034 |
| Death or MI | | | | |
| 48 hours |
94 (9.2%) |
57 (5.5%) |
0.597 (0.435, 0.82) |
0.0013 |
| 30 days |
104 (10.2%) |
66 (6.3%) |
0.625 (0.465, 0.84) | 0.0016 |
| *Eptifibatide injection was administered as 180 mcg/kg boluses at times 0 and 10 minutes and an infusion at 2 mcg/kg/min. |
The need for thrombotic “bailout” was significantly reduced with eptifibatide injection at 48 hours (2.1% for placebo, 1% for eptifibatide injection; p=0.029). Consistent with previous studies of GP IIb/IIIa inhibitors, most of the benefit achieved acutely with eptifibatide injection was in the reduction of MI. Eptifibatide injection reduced the occurrence of MI at 48 hours from 9% for placebo to 5.4% (p=0.0015) and maintained that effect with significance at 30 days.
There was no treatment difference with respect to sex in ESPRIT. Eptifibatide injection reduced the incidence of the primary endpoint in both men (95% confidence limits for relative risk: 0.54, 1.07) and women (0.24, 0.72) at 48 hours.
Follow-up (12-month) mortality data were available for 2,024 patients (1,017 on eptifibatide injection) enrolled in the ESPRIT trial (98.1% of the initial enrollment). Twelve-month clinical event data were available for 1,964 patients (988 on eptifibatide injection), representing 95.2% of the initial enrollment. As shown in Table 9, the treatment effect of eptifibatide injection seen at 48 hours and 30 days appeared preserved at 6 months and 1 year. Most of the benefit was in reduction of MI.
Table 9: Clinical Events at 6 Months and 1 Year in the ESPRIT Study
|
Placebo
(n=1,024) |
Eptifibatide injection
(n=1,040) |
Hazard Ratio
(95% CI) |
| Death, MI, or Target Vessel Revascularization | | | |
6 Months | 187 (18.5%) |
146 (14.3%) | 0.744 (0.599, 0.924) |
1 Year | 222 (22.1%) |
178 (17.5%) | 0.762 (0.626, 0.929) |
| Death, MI | | | |
6 Months | 117 (11.5%) |
77 (7.4%) | 0.631 (0.473, 0.841) |
1 Year | 126 (12.4%) |
83 (8%) | 0.63 (0.478, 0.832) |
| Percentages are Kaplan-Meier event rates. |